
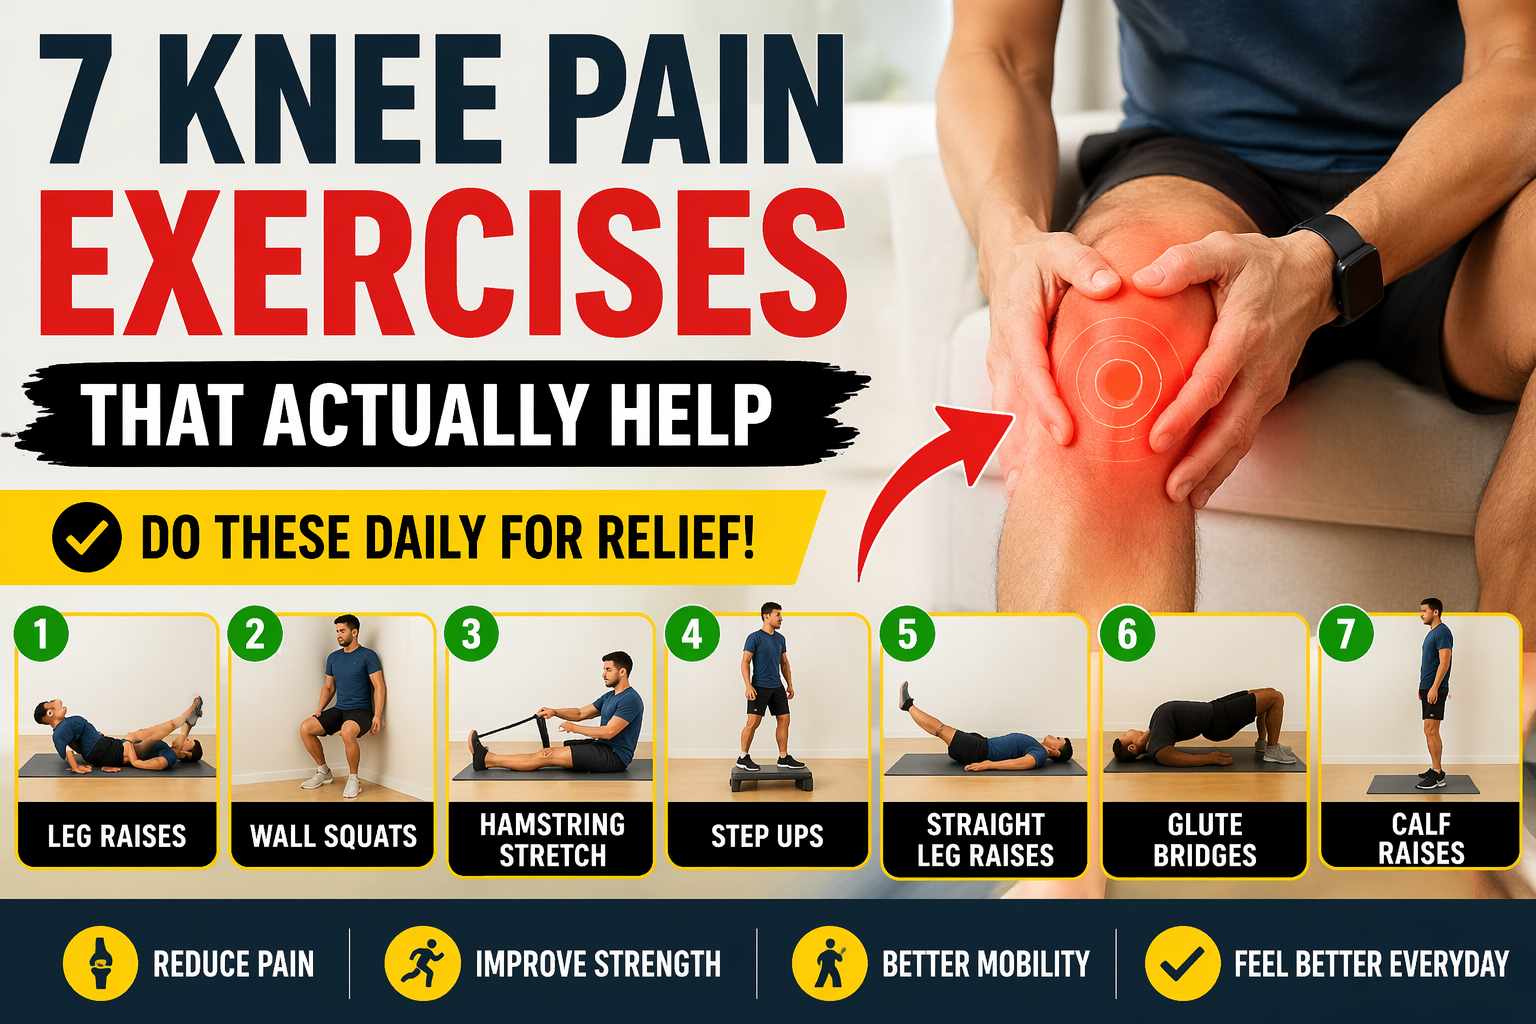
Try these 7 knee pain exercises daily for real relief. Step-by-step instructions, a weekly routine, and tips to strengthen and protect your knees.
Knee pain has a way of shrinking your life. Stairs become a calculation. A walk around the block turns into a decision you have to think about. Getting up from a low chair comes with a small wince you have learned to hide. If that sounds familiar, you are far from alone: knee pain is one of the most common musculoskeletal complaints among adults, and it affects people in their twenties just as it does people in their seventies, though the causes often differ.
The good news, backed by a large and consistent body of research, is that for many of the most common causes of knee pain, targeted exercise is not just safe, it is one of the most effective tools available. Strengthening the muscles that support the knee, particularly the quadriceps, hamstrings, glutes, and hip stabilizers, reduces the load the joint itself has to absorb. Improving flexibility and mobility around the knee and hip can ease strain. And movement itself, done correctly, tends to reduce pain and stiffness over time rather than making things worse, which is the opposite of what many people instinctively assume.
This guide walks you through 7 knee pain exercises that actually help, chosen because they are supported by physical therapy research and commonly recommended by orthopedic and sports medicine professionals for a wide range of knee issues, from mild stiffness to osteoarthritis to post-injury recovery. You will find step-by-step instructions, sets and reps, common mistakes to avoid, a full daily and weekly routine, modifications for different fitness levels and pain levels, and clear guidance on when knee pain needs a doctor’s attention rather than a home exercise program.
Important note: This article is for general education and is not medical advice. It does not diagnose, treat, or replace care from a licensed healthcare provider. If you have significant, worsening, or unexplained knee pain, a recent injury, swelling, instability, or any of the warning signs listed later in this guide, please see a doctor or physical therapist before starting any new exercise program. Stop any exercise that causes sharp, worsening pain.
Table of Contents
- Why Exercise Helps Knee Pain (and Why Rest Alone Often Doesn’t)
- Common Causes of Knee Pain This Routine Can Help With
- When You Should See a Doctor First
- How to Prepare Before You Start
- The 7 Knee Pain Exercises That Actually Help
- How to Build Your Daily and Weekly Routine
- Warm-Up and Cool-Down Routines for Knee Health
- Modifications by Fitness Level and Pain Level
- Common Mistakes That Make Knee Exercises Less Effective (or Risky)
- Exercises and Movements to Be Cautious With
- Supporting Your Knees Beyond Exercise
- Knee Pain Exercises for Specific Situations
- How to Track Your Progress
- Troubleshooting: What to Do If Exercises Hurt
- Understanding Your Knee: A Quick Anatomy Primer
- A Closer Look at Knee Osteoarthritis and Exercise
- Common Myths About Knee Pain, Debunked
- Nutrition and Lifestyle Factors Often Discussed Alongside Knee Health
- How This Compares to Other Common Knee Pain Treatments
- Building a Knee-Friendly Exercise Toolkit
- A 4-Week Sample Progression Plan
- Signs Your Routine Is Working
- Frequently Asked Questions About Knee Pain Exercises
- A Closer Look at Patellofemoral Pain Syndrome
- A Closer Look at IT Band Syndrome
- Glossary: Key Terms Used in This Guide
- Pre-Exercise Safety Checklist
- 14 Daily Habits for Long-Term Knee Health
- Three Common Scenarios and How to Adapt Your Routine
- A Few More Frequently Asked Questions
- Two Extra Mini-Routines: Morning and Desk Versions
- Matching Exercises to Your Specific Pain Pattern
- What to Include in Your Own Printable Quick-Reference Sheet
- Distinguishing Similar-Sounding Knee Conditions
- Putting It All Together: A Realistic Month-by-Month Outlook
- Combining This Routine With Other Forms of Exercise
- An Equipment-Free Travel Version of the Routine
- Key Takeaways
- How This Guide Was Informed
- A Few More Questions Worth Addressing
- Final Thoughts: Building Stronger, More Resilient Knees
Why Exercise Helps Knee Pain (and Why Rest Alone Often Doesn’t)
It feels counterintuitive. Your knee hurts, so your instinct is to protect it by moving it less. For an acute injury in the first day or two, some rest is appropriate. But for most ongoing, chronic, or recurring knee pain, particularly pain related to arthritis, overuse, mild instability, or general deconditioning, research consistently shows that movement and targeted strengthening lead to better outcomes than prolonged rest.
The Muscle-Support Theory
The knee joint itself is just bone, cartilage, ligaments, and the kneecap gliding in its groove. It has very little ability to protect itself. The muscles surrounding it, especially the quadriceps at the front of the thigh, the hamstrings at the back, the glutes at the hip, and the smaller stabilizing muscles around the hip and ankle, do the real work of controlling how force moves through the joint during walking, climbing stairs, and standing up from a chair.
When these muscles are weak, more of the mechanical load lands directly on the joint structures, the cartilage, the meniscus, and the ligaments, instead of being absorbed and controlled by muscle. Over time, this can increase pain and may contribute to further wear. Strengthening these muscles effectively gives the knee better “shock absorbers,” reducing the direct load it has to withstand with each step.
What the Research Shows
Multiple systematic reviews and clinical guidelines, including those from major orthopedic and rheumatology organizations, identify exercise therapy as a first-line, evidence-supported treatment for knee osteoarthritis, the most common cause of chronic knee pain in older adults. Studies on strengthening programs, particularly quadriceps-focused strengthening, have repeatedly shown reductions in pain and improvements in function, in some cases comparable to or better than what is achieved with some pain medications, without the associated side effects. Research on patellofemoral pain syndrome, a very common cause of knee pain in younger, active people, similarly shows that hip and quadriceps strengthening programs are more effective than rest or passive treatments alone.
Why Rest Alone Often Backfires
Prolonged inactivity due to knee pain often triggers a frustrating cycle: less movement leads to weaker muscles, which leads to more load being placed directly on the joint during the movement you do perform, which leads to more pain, which leads to even less movement. Over weeks and months, this cycle can leave someone significantly deconditioned, with a knee that hurts more, not less, than when they started resting it. Breaking this cycle with appropriate, graded exercise is one of the most well-supported interventions in musculoskeletal health.
“Hurt” Does Not Always Mean “Harm”
This is one of the most important concepts in modern rehabilitation science. Some mild discomfort or achiness during and shortly after starting a new exercise program is common and does not necessarily indicate that damage is occurring. Many physical therapists use general pain guidelines, such as keeping exercise-related discomfort at a mild level (often described as no more than about 3 to 4 out of 10 on a pain scale) that settles down within an hour or so after exercise, as a rough gauge for whether an exercise is appropriately challenging versus excessive. Sharp, severe, or worsening pain, or pain that persists or increases significantly after exercise, is different and is a signal to stop and reassess, ideally with a healthcare professional.
What This Routine Is (and Is Not) Designed to Do
This routine focuses on strengthening and mobility exercises that are widely used in physical therapy settings for common sources of knee pain. It is designed to be approachable for home use, requiring minimal or no equipment. It is not a replacement for a personalized physical therapy assessment, which can identify the specific cause of your pain and tailor a program accordingly. Think of this guide as a well-researched starting point, not a diagnosis or a substitute for professional care.
Common Causes of Knee Pain This Routine Can Help With
Understanding what might be behind your knee pain can help you use this routine more effectively and know what to expect. This is general information, not a diagnostic tool; only a healthcare provider can diagnose the specific cause of your knee pain.
Knee Osteoarthritis
Osteoarthritis involves the gradual breakdown of cartilage within the joint, leading to pain, stiffness (especially after rest or in the morning), and sometimes swelling. It is extremely common, particularly in adults over 50, though it can occur earlier. Exercise, particularly strengthening of the muscles around the knee and hip, is a core recommended treatment in virtually every major clinical guideline for knee osteoarthritis, alongside weight management (when relevant) and activity modification.
Patellofemoral Pain Syndrome (“Runner’s Knee”)
This refers to pain around or behind the kneecap, often related to how the kneecap tracks within its groove during movement. It is common in runners, cyclists, and other active individuals, as well as people who sit for long periods. Weakness in the hip and quadriceps muscles is strongly associated with this condition, which is why hip- and quad-focused strengthening is a central part of its treatment.
IT Band Syndrome
The iliotibial (IT) band runs along the outside of the thigh from the hip to just below the knee. When it becomes tight or the surrounding muscles (particularly the glutes) are weak, it can rub against the outside of the knee, causing pain, especially during repetitive activities like running or cycling. Hip strengthening and targeted stretching are commonly recommended approaches.
General Deconditioning and Overuse
Sometimes knee pain develops simply from a mismatch between activity level and strength, such as a sudden increase in walking, standing, or exercise after a period of inactivity, or from muscle weakness that has developed gradually over months or years of a sedentary lifestyle. This type of pain often responds very well to a gradual, consistent strengthening program.
Mild Ligament Strains (After Clearance From a Provider)
Once an acute ligament injury has been evaluated and a healthcare provider has confirmed that controlled exercise is appropriate (this varies significantly depending on the severity and type of injury), gentle strengthening exercises are often part of the recovery process to restore strength and stability. This routine is not appropriate as a first response to a new, acute injury; see the next section for guidance on when to seek care first.
Post-Surgical Recovery (With Provider Guidance)
People recovering from certain knee surgeries, such as meniscus repair or even knee replacement, often follow structured exercise programs that include many of the same movement patterns discussed in this guide, though exact timing, progression, and restrictions should always be directed by your surgeon or physical therapist, since post-surgical protocols vary significantly.
Weak Hips Contributing to Knee Strain
An often-overlooked contributor to knee pain is weakness at the hip, specifically the gluteus medius, a muscle on the side of the hip that helps control the position of the thigh and knee during walking and single-leg activities. When this muscle is weak, the knee can drift inward during movement, increasing stress on the joint. This is part of why several of the exercises in this routine target the hips as much as the knee itself.
EOF wc -w /mnt/user-data/outputs/7-knee-pain-exercises-that-actually-help.md—
When You Should See a Doctor First
This routine is designed for common, non-emergency knee pain, the kind that builds gradually, comes and goes with activity, or has been present for a while without a specific traumatic cause. Certain signs and situations call for professional evaluation before starting any exercise program.
Seek Prompt Medical Care If You Experience:
- A recent, specific injury, such as a fall, a twisting injury during sports, or a direct blow to the knee, especially if you heard or felt a pop at the time of injury.
- Inability to bear weight on the leg, or a feeling that the knee is giving way or buckling.
- Significant swelling that develops quickly, particularly within hours of an injury.
- Visible deformity of the knee or an inability to fully straighten or bend it.
- Severe pain that is not improving or is worsening.
- Signs of infection, such as redness, warmth, significant swelling, and fever.
- Numbness, tingling, or weakness in the leg or foot.
- A knee that is locked and cannot move through its normal range.
Schedule a Non-Urgent Medical Evaluation If You Have:
- Knee pain that has persisted for more than a few weeks without improvement.
- Pain that is steadily worsening despite rest and basic home care.
- Pain accompanied by unexplained weight loss, fever, or feeling generally unwell.
- A history of cancer, with new or unexplained bone or joint pain.
- Significant difficulty with daily activities due to knee pain, such as walking, climbing stairs, or standing from a chair.
- Pain that wakes you up at night or is present even at rest.
- Known or suspected inflammatory arthritis (such as rheumatoid arthritis), with a new or worsening knee flare.
Who Should Get Clearance Before Starting Any New Exercise Program
- Anyone recovering from recent knee surgery, who should follow their surgeon’s or physical therapist’s specific post-operative protocol rather than this general guide.
- Anyone with a diagnosed ligament tear, meniscus tear, or fracture that has not yet been evaluated for whether exercise is appropriate.
- Anyone with significant heart, lung, or other health conditions that affect exercise tolerance generally.
- Anyone who is pregnant, since some exercise modifications may be needed and are best guided by a healthcare provider.
- Older adults with multiple health conditions or a history of falls, who may benefit from a supervised program, at least initially.
Why Seeing a Physical Therapist Can Be Valuable, Even for Mild Pain
A physical therapist can assess your specific movement patterns, identify which muscles are weak or which movement habits may be contributing to your pain, and tailor a program more precisely than any general guide can. For persistent or recurring knee pain, even if it feels mild, an initial evaluation can help ensure you are doing the right exercises for your specific situation, and can catch issues a general article like this one cannot account for.
A Reasonable Approach If You Are Unsure
If your knee pain is mild, has been present for a while, is not accompanied by any of the warning signs above, and tends to improve somewhat with gentle movement, it is generally reasonable to try a gentle, gradual exercise approach like the one in this guide, paying close attention to how your knee responds. If pain does not improve within two to three weeks of consistent, appropriate exercise, or if it worsens at any point, that is a clear signal to see a healthcare provider rather than continuing to push through on your own.
How to Prepare Before You Start
A little preparation makes this routine safer, more comfortable, and easier to stick with.
What You’ll Need
- A supportive, flat surface to exercise on, such as a yoga mat or carpeted floor.
- A sturdy chair for support during several of the exercises.
- A wall for balance support in a few variations.
- Comfortable clothing that allows a full range of motion at the hip and knee.
- Supportive shoes, or a flat, stable bare-foot surface, depending on the exercise.
- Optional equipment: a resistance band (light to medium resistance) and a small pillow or rolled towel, both of which are used in some exercise variations but are not required to begin.
Setting Realistic Expectations
Most people do not feel dramatically better after a single session. Research on strengthening programs for knee pain generally shows meaningful improvement over a period of 6 to 12 weeks of consistent exercise, with some people noticing initial improvements in the first 2 to 3 weeks. Approach this as a gradual process, not a quick fix, and expect some fluctuation along the way.
Choosing the Right Time of Day
Many people find that knees feel stiffer first thing in the morning, particularly with arthritis-related pain, and may prefer to exercise later in the day once they have “warmed up” through normal movement. Others find a consistent morning routine easier to stick with. There is no universally “correct” time; choose what you can realistically maintain daily or near-daily.
A Note on Pain Medication and Exercise
If you typically take an over-the-counter or prescribed pain reliever, some people find it helpful to time their exercise session for when medication is providing comfortable relief, making movement more comfortable and effective. This is a personal and sometimes medical decision; if you have specific questions about how medication timing relates to exercise, your doctor or pharmacist can advise based on your specific situation.
Building the Habit
Because consistency matters more than intensity for this type of program, consider:
- Attaching the routine to an existing habit, such as right after brushing your teeth or during a regular TV program.
- Keeping your mat or exercise space set up and visible, rather than needing to retrieve equipment each time.
- Starting with a shorter version of the routine if the full version feels overwhelming, and building up gradually.
- Tracking your sessions, even with a simple checkmark on a calendar, which research on habit formation shows can meaningfully improve consistency.
The 7 Knee Pain Exercises That Actually Help
These seven exercises were selected because they target the muscle groups most consistently linked to knee pain relief and function in physical therapy research: the quadriceps, hamstrings, glutes, and hip stabilizers, along with knee range of motion. Each includes step-by-step instructions, starting sets and reps, progression options, common mistakes, and notes on what the exercise specifically helps with.
A general starting guideline: Begin with the lower end of the suggested repetition range, and only on one side if that is more comfortable, especially if you are new to exercise or currently in a flare-up of pain. Progress gradually over days and weeks, not all at once.
Exercise 1: Quad Sets (Isometric Quadriceps Contraction)
What it helps with: This is often the very first exercise introduced in physical therapy for almost any knee condition, including after surgery, because it strengthens the quadriceps without any joint movement, making it extremely gentle and appropriate even for significant pain or very early-stage recovery.
How to do it:
- Sit or lie down with your leg straight out in front of you. A small rolled towel placed under the knee can help, especially if lying flat is uncomfortable.
- Press the back of your knee down into the floor or towel, tightening the muscle on the top of your thigh (the quadriceps) as if trying to straighten a bent knee further, even though your leg is already straight.
- You should see your kneecap shift slightly upward as the muscle contracts.
- Hold the contraction for 5 to 10 seconds.
- Relax completely for a few seconds.
- Repeat.
Starting sets and reps: 10 repetitions, holding each for 5 to 10 seconds, 2 to 3 times per day.
Progression: Increase the hold time to 10 to 15 seconds, or increase repetitions to 15 to 20 per set as it becomes easier.
Common mistakes:
- Holding your breath during the contraction. Breathe normally throughout.
- Moving the leg instead of simply contracting the muscle with the leg staying still.
- Contracting so hard that it causes pain; the effort should feel firm but not forceful enough to hurt.
Why it works: Because there is no joint movement involved, this exercise allows you to begin strengthening the quadriceps, one of the most important muscles for knee support, even when movement-based exercises are too uncomfortable. It is frequently used as a foundation before progressing to more dynamic exercises.
Exercise 2: Straight Leg Raises
What it helps with: Builds on the quad set by adding controlled movement, further strengthening the quadriceps and hip flexors without bending the knee, which makes it one of the gentlest ways to strengthen the muscles that support the kneecap and joint.
How to do it:
- Lie on your back on a mat or firm surface. Bend one knee with your foot flat on the floor, and keep the other leg straight.
- Tighten the quadriceps of the straight leg (as in the quad set above) before lifting it.
- Slowly raise the straight leg to about the height of the opposite bent knee, keeping it fully straight throughout.
- Hold briefly at the top, for 1 to 2 seconds.
- Slowly lower the leg back down with control, rather than letting it drop.
- Complete all repetitions on one side before switching, or alternate sides, based on preference.
Starting sets and reps: 2 sets of 10 repetitions per leg.
Progression: Add a light ankle weight (starting around 1 to 2 pounds / 0.5 to 1 kg) once 2 sets of 15 feels easy without the weight, or slow down the tempo (for example, a 3-second lift and a 3-second lower) to increase difficulty without added weight.
Common mistakes:
- Letting the knee bend during the lift, which shifts effort away from the quadriceps.
- Arching the lower back excessively; keep the lower back gently pressed toward the floor, and consider bending the resting leg’s knee (as described) to help support this.
- Lifting too high, past the height of the opposite knee, which can increase strain on the hip flexors without added benefit to the knee muscles.
- Letting the leg drop quickly on the way down instead of lowering with control, which reduces the strengthening benefit.
Why it works: Research on patellofemoral pain and general knee strengthening programs consistently includes straight leg raises as a foundational exercise, since it builds genuine quadriceps strength while keeping the knee joint itself in a pain-free, fully extended position throughout the movement.
Exercise 3: Wall Sits (or Mini Wall Sits)
What it helps with: Builds functional quadriceps and overall lower-body strength in a position similar to how the knee is loaded during daily activities like standing from a chair, making it particularly useful for improving function in day-to-day movements.
How to do it:
- Stand with your back against a wall, feet shoulder-width apart and positioned about 12 to 18 inches (30 to 45 cm) out from the wall.
- Slowly slide your back down the wall by bending your knees, as if sitting into an invisible chair, only as far as is comfortable. For many people starting out, this means bending the knees only slightly, perhaps 20 to 30 degrees, rather than aiming for a full 90-degree position right away.
- Keep your knees aligned over your ankles, not pushing forward past your toes, and keep your weight balanced through your whole foot.
- Hold the position, keeping your core engaged and breathing normally.
- Slowly slide back up to standing.
Starting sets and reps: Hold for 10 to 15 seconds, repeat 3 to 5 times, resting between holds.
Progression: Gradually increase the hold time (working toward 30 to 60 seconds) and/or increase the depth of the knee bend as strength improves, always staying within a pain-free or mildly uncomfortable range.
Common mistakes:
- Going too deep too soon, which places more load on the knees than the current strength level supports.
- Letting the knees cave inward toward each other; keep them tracking in line with the toes.
- Pushing the knees out past the toes excessively, which can increase strain; a slight forward position is normal, but the shin should stay relatively vertical for most people.
- Holding the breath; breathe steadily throughout the hold.
Why it works: Wall sits train the quadriceps isometrically (without the joint moving through its full range) in a weight-bearing position that closely mirrors functional movements like standing up and sitting down, which tends to translate well into real-world improvements in daily activities that involve the knees.
Exercise 4: Step-Ups (Using a Low Step or Stair)
What it helps with: Directly strengthens the quadriceps, glutes, and hip stabilizers in a functional pattern that mimics climbing stairs, one of the most commonly reported difficult activities for people with knee pain, making this exercise particularly effective for improving real-world function.
How to do it:
- Stand facing a low, stable step, such as the bottom stair of a staircase or a sturdy step platform, starting with a low height (around 4 to 6 inches / 10 to 15 cm) if you are new to this exercise.
- Place one foot fully on the step.
- Press through that foot to lift your body up onto the step, bringing the other foot up to meet it, or tapping it lightly on the step before stepping back down, depending on your preference and balance.
- Focus on using the muscles of the leg that is stepping up to do the work, rather than pushing off heavily with the trailing leg.
- Step back down with control, leading with the same leg you stepped up with, or alternating as preferred.
- Hold onto a wall, railing, or sturdy furniture for balance support if needed, especially when starting out.
Starting sets and reps: 2 sets of 8 to 10 repetitions per leg.
Progression: Increase the step height gradually (toward a standard stair height of about 7 to 8 inches / 18 to 20 cm) as strength and confidence improve, or add light hand weights once the basic movement feels controlled and comfortable.
Common mistakes:
- Letting the knee cave inward as you step up; focus on keeping the knee tracking in line with the second toe.
- Using momentum or pushing heavily off the back leg instead of controlling the movement with the stepping leg.
- Choosing a step that is too high before building adequate strength, which can increase strain and reduce control.
- Rushing the movement; a slower, controlled pace builds more strength and stability than a fast, uncontrolled one.
Why it works: Because step-ups closely replicate the mechanics of stair climbing, a commonly painful activity for people with knee issues, this exercise builds strength specifically in the pattern that tends to cause the most difficulty, which often translates into a more noticeable real-world improvement than more abstract exercises.
Exercise 5: Hamstring Curls (Standing or Using a Resistance Band)
What it helps with: Strengthens the hamstrings, which work alongside the quadriceps to stabilize the knee joint; a balance between quadriceps and hamstring strength is considered important for overall knee health and injury prevention.
How to do it (standing version, no equipment needed):
- Stand holding onto a wall, chair, or counter for balance.
- Slowly bend one knee, bringing your heel up toward your glutes, keeping your thighs aligned next to each other (avoid letting the bent knee drift forward or to the side).
- Hold briefly at the top of the movement.
- Slowly lower the foot back down with control.
How to do it (with a resistance band, for added challenge):
- Secure a resistance band around a sturdy, low anchor point (such as a heavy piece of furniture) and loop the other end around your ankle.
- Stand facing away from the anchor point with the band taut.
- Perform the same curling motion as above, bending the knee against the resistance of the band.
Starting sets and reps: 2 sets of 10 to 12 repetitions per leg.
Progression: Increase repetitions, add a resistance band if using the standing bodyweight version, or increase band resistance if already using one.
Common mistakes:
- Letting the hips rotate or shift to compensate instead of isolating the movement to the knee and hamstring.
- Moving too quickly, which reduces muscle engagement and control.
- Allowing the standing (support) leg’s knee to lock out harshly; keep a slight, soft bend in the standing knee.
Why it works: The hamstrings play an important role in controlling knee movement and stability, particularly during activities that involve bending and decelerating, such as walking downhill or down stairs. Strengthening them alongside the quadriceps helps create more balanced support around the joint.
Exercise 6: Clamshells
What it helps with: Targets the gluteus medius, a hip muscle that plays a key role in controlling knee alignment during walking, stair climbing, and single-leg activities; weakness here is strongly associated with knee pain, particularly patellofemoral pain and IT band-related pain.
How to do it:
- Lie on your side on a mat, with your hips and knees bent to about a 45-degree angle, knees stacked on top of each other, and your head resting on your lower arm or a pillow for comfort.
- Keeping your feet together and touching, slowly lift your top knee upward, like opening a clamshell, while keeping your hips stacked and still, without rolling your pelvis backward.
- Hold briefly at the top of the movement.
- Slowly lower the knee back down with control.
Starting sets and reps: 2 sets of 12 to 15 repetitions per side.
Progression: Add a light resistance band looped just above the knees once the basic movement feels controlled, or increase repetitions.
Common mistakes:
- Rolling the hips backward to “cheat” the movement higher, which shifts the work away from the target muscle. Keep the hips stacked throughout.
- Moving too fast, using momentum rather than controlled muscle engagement.
- Lifting the knee only a small amount due to tightness through the hips; a smaller, controlled range of motion with proper form is more valuable than a larger range with compensatory movement.
Why it works: Because knee alignment during movement is significantly influenced by hip control, strengthening the gluteus medius through clamshells helps prevent the inward knee collapse pattern that is commonly linked to knee pain, particularly during single-leg activities like walking, stair climbing, and standing on one leg.
Exercise 7: Heel Slides (Gentle Knee Flexion and Extension)
What it helps with: Gently restores and maintains knee range of motion, which is particularly important for stiffness related to arthritis or after a period of reduced activity; it is often one of the most comfortable movement-based exercises for people dealing with significant stiffness or discomfort.
How to do it:
- Lie on your back with both legs straight.
- Slowly slide the heel of one leg along the floor toward your glutes, bending the knee as far as is comfortable, without forcing the movement or pushing into sharp pain.
- Hold the bent position briefly if comfortable.
- Slowly slide the heel back down to the starting straight-leg position.
Starting sets and reps: 10 to 15 repetitions per leg, performed slowly and with full attention to how the knee feels throughout.
Progression: As range of motion and comfort improve, work toward a deeper bend, and consider adding a very light resistance (such as gently assisting the stretch with your hands at the end range) if advised appropriate for your specific situation.
Common mistakes:
- Forcing the knee into a deeper bend than is comfortable, which can increase irritation rather than help.
- Moving quickly instead of slowly and deliberately, which reduces the gentle mobilizing effect of the exercise.
- Holding your breath, particularly if the stretch at end range feels intense; breathe steadily throughout.
Why it works: Maintaining full, comfortable range of motion in the knee is an important but sometimes overlooked part of managing knee pain, particularly for arthritis-related stiffness. Heel slides provide a very low-impact way to gently move the joint through its range without significant loading, which can help reduce stiffness and maintain mobility over time.
A Quick Reference Summary of the 7 Exercises
| Exercise | Primary Target | Starting Volume | Equipment |
|---|---|---|---|
| 1. Quad sets | Quadriceps (isometric) | 10 reps x 5–10 sec hold, 2–3x/day | None |
| 2. Straight leg raises | Quadriceps, hip flexors | 2 sets of 10 per leg | None (ankle weight optional later) |
| 3. Wall sits | Quadriceps (functional) | 3–5 holds of 10–15 sec | Wall |
| 4. Step-ups | Quads, glutes, hip stabilizers | 2 sets of 8–10 per leg | Low step or stair |
| 5. Hamstring curls | Hamstrings | 2 sets of 10–12 per leg | None (band optional later) |
| 6. Clamshells | Gluteus medius (hip) | 2 sets of 12–15 per side | None (band optional later) |
| 7. Heel slides | Knee range of motion | 10–15 reps per leg | None |
How to Build Your Daily and Weekly Routine
Consistency matters more than any single session. Here is how to structure these seven exercises into a sustainable daily and weekly practice.
The Daily “Quick Routine” (About 10 to 12 Minutes)
For days when you want something simple and sustainable, or when starting out, this shortened version hits the key movements:
- Quad sets: 10 reps, 5-second holds
- Straight leg raises: 1 set of 10 per leg
- Heel slides: 10 reps per leg
- Clamshells: 1 set of 12 per side
- Wall sit: 3 holds of 10 to 15 seconds
This quick version can reasonably be done daily, even on days when you also do the full routine described below, since the loads involved are light and designed to be gentle on the joint.
The Full Routine (About 20 to 25 Minutes)
For 3 to 5 days per week, aim to complete all seven exercises at the fuller volume described in the previous section:
- Quad sets: 10 reps, 5 to 10-second holds, done once as part of this session (in addition to any other times during the day)
- Straight leg raises: 2 sets of 10 per leg
- Wall sits: 3 to 5 holds of 10 to 15 seconds
- Step-ups: 2 sets of 8 to 10 per leg
- Hamstring curls: 2 sets of 10 to 12 per leg
- Clamshells: 2 sets of 12 to 15 per side
- Heel slides: 10 to 15 reps per leg
A Sample Weekly Schedule
| Day | Routine |
|---|---|
| Monday | Full routine |
| Tuesday | Quick routine, or rest if feeling fatigued |
| Wednesday | Full routine |
| Thursday | Quick routine |
| Friday | Full routine |
| Saturday | Quick routine or gentle walk |
| Sunday | Rest, or light stretching only |
This schedule provides consistent, near-daily movement while allowing some lighter days to prevent overuse, which matters particularly in the early weeks as your body adapts to a new exercise routine.
Should You Exercise Both Legs, Even If Only One Hurts?
In most cases, yes, exercising both legs is generally recommended, even if pain is isolated to one knee. This helps maintain overall strength and balance, and in many cases, some degree of weakness is actually present on both sides, even if pain is only noticeable on one. If one side is significantly more painful, you can still perform exercises on that side within a comfortable range, or temporarily reduce the volume on the painful side while continuing full volume on the other, based on how your body responds.
How Long Before You Can Expect to Notice a Difference?
Most research on structured strengthening programs for knee pain shows measurable improvements in pain and function within about 6 to 8 weeks of consistent exercise, with some people noticing initial improvements, such as reduced stiffness or easier stair climbing, within the first 2 to 3 weeks. Results vary significantly based on the underlying cause of pain, consistency, and individual factors. Patience and consistency tend to matter more than intensity.
What to Do If You Miss Days
Missing an occasional day or even several days due to illness, travel, or simply life getting busy is completely normal and does not erase prior progress in any meaningful way. Simply resume the routine at roughly the same volume you left off at, or slightly lower if you have been away for more than a week or two, and build back up from there.
Warm-Up and Cool-Down Routines for Knee Health
Bookending your exercise session with a brief warm-up and cool-down can improve comfort and may reduce the risk of excessive soreness, particularly as you are building a new routine.
A Simple 5-Minute Warm-Up
- March in place, lifting your knees to a comfortable height, for 1 to 2 minutes. This gently increases blood flow to the legs.
- Ankle circles, 10 in each direction per foot, performed seated or standing.
- Gentle knee bends, standing and holding onto a support if needed, bending the knees slightly and straightening, for about 10 repetitions, to begin gently moving the joint before more targeted exercise.
- Hip circles, standing with hands on hips, making gentle circles with the hips in each direction, 5 to 10 times per direction, to loosen the hip joints that work closely with the knees.
A Simple 5-Minute Cool-Down (Gentle Stretches)
After your exercise session, gentle stretching can help with comfort and flexibility. Hold each stretch to a point of mild tension, never pain, and breathe steadily throughout.
Quadriceps stretch (standing or lying):
- Standing and holding onto a wall or chair for balance, bend one knee and bring your heel toward your glutes, holding your ankle or pant leg with your hand (or using a towel looped around your ankle if you cannot comfortably reach).
- Keep your knees close together and your standing leg slightly bent.
- Hold for 20 to 30 seconds, feeling a gentle stretch along the front of the thigh.
- Switch sides.
Hamstring stretch:
- Sit on the edge of a sturdy chair or on the floor with one leg extended straight in front of you and the other bent with the foot flat on the floor.
- Keeping your back relatively straight, gently hinge forward from the hips until you feel a mild stretch along the back of the extended thigh.
- Hold for 20 to 30 seconds.
- Switch sides.
Calf stretch:
- Stand facing a wall with your hands against it for support.
- Step one foot back, keeping that back leg straight and the heel pressed into the floor, while bending the front knee slightly.
- Lean gently into the wall until you feel a stretch in the calf of the back leg.
- Hold for 20 to 30 seconds.
- Switch sides.
IT band and hip stretch:
- Standing, cross one leg behind the other.
- Lean your upper body gently to the side, away from the back leg, reaching the same-side arm overhead, until you feel a mild stretch along the outside of the hip and thigh of the back leg.
- Hold for 20 to 30 seconds.
- Switch sides.
Why Warming Up and Cooling Down Matters
A brief warm-up increases blood flow to the muscles and can make the subsequent strengthening exercises feel more comfortable and effective, while a gentle cool-down stretch can help ease any tightness that builds during exercise and supports overall flexibility, which plays a role in how well the knee moves through its range during daily activities.
Modifications by Fitness Level and Pain Level
This routine can be adjusted significantly based on where you are starting from. Use the guidance below to find your appropriate starting point.
For Significant Current Pain or a Recent Flare-Up
- Focus primarily on Exercise 1 (quad sets) and Exercise 7 (heel slides), both of which are very gentle and widely used even in early rehabilitation settings.
- Perform these multiple times per day in short sessions (even 5 minutes) rather than one longer session.
- Hold off on wall sits, step-ups, and standing hamstring curls until pain has settled to a more manageable, mild level.
- Consider applying ice for 15 to 20 minutes after exercise if swelling or significant discomfort is present, and elevate the leg when resting if swelling is noticeable. (General comfort measure; not a substitute for medical evaluation if swelling is significant or persistent.)
For Mild to Moderate Pain, Able to Walk Comfortably
- Begin with the full routine at the lower end of the suggested repetition ranges.
- Perform the quick routine daily, and the full routine 3 to 4 times per week.
- Pay close attention to how your knee feels in the hours after exercise, and adjust volume based on that response.
For Minimal Pain, Looking to Build Strength and Prevent Future Issues
- Begin at the higher end of the suggested repetition ranges, or move more quickly through the progression options described for each exercise.
- Consider adding light resistance (ankle weights, resistance bands) sooner, once basic form is comfortable and controlled.
- Perform the full routine 4 to 5 times per week as part of a general strength maintenance practice.
For Older Adults or Those New to Exercise
- Hold onto a sturdy support (wall, chair, or counter) for all standing exercises, particularly step-ups and wall sits, until balance and confidence improve.
- Start with fewer repetitions than suggested (such as 5 to 8 instead of 10 to 12) and build up gradually over several weeks.
- Consider performing exercises seated where possible (such as straight leg raises from a seated position with the leg extended) if lying on the floor is difficult or uncomfortable.
- A chair-based variation of several exercises is described later in the “Knee Pain Exercises for Specific Situations” section.
For Athletes or Very Active Individuals
- This routine serves well as a foundational strengthening base, but may need to be supplemented with more advanced, sport-specific exercises as part of a complete return-to-activity program, ideally guided by a physical therapist or athletic trainer familiar with your specific sport and goals.
- Progress volume and resistance more aggressively, following the progression notes for each exercise, while still respecting pain and fatigue signals.
Adjusting for One-Sided vs. Both-Sided Pain
If pain is present in only one knee, perform the full routine on both sides as described earlier, adjusting volume on the more painful side as needed based on comfort. If both knees are affected, the same routine applies to both sides; there is no need for a fundamentally different approach, though you may find one side needs to progress more slowly than the other, which is entirely normal.
Common Mistakes That Make Knee Exercises Less Effective (or Risky)
Avoiding these common errors will help you get more benefit from this routine while reducing unnecessary discomfort or setbacks.
Mistake 1: Doing Too Much, Too Soon
Jumping straight into high repetitions, added resistance, or the most advanced progression of each exercise, especially if you have been inactive or in significant pain, often leads to excessive soreness that can discourage continued effort, or in some cases, a genuine flare-up of pain. Fix: Start conservatively, even if it feels “too easy” at first, and progress gradually over 1 to 2 weeks before adding more volume or resistance.
Mistake 2: Inconsistent Practice
Doing the full routine intensely for one session, then skipping several days, then trying again, tends to produce less consistent results than a steadier, more moderate daily or near-daily practice. Fix: Prioritize the shorter “quick routine” on busy days rather than skipping entirely, since consistency is one of the most important factors in long-term improvement.
Mistake 3: Poor Form to “Get Through” Repetitions
Rushing through repetitions, using momentum, or allowing compensatory movements (such as the hip rolling back during clamshells, or the knee caving in during step-ups) reduces the effectiveness of the exercise and can place strain on structures it was not meant to target. Fix: Prioritize quality over quantity; a smaller number of well-executed repetitions is more valuable than a larger number performed with poor form.
Mistake 4: Ignoring Pain Signals Entirely
Some people, particularly those eager to recover quickly, push through sharp or worsening pain, assuming “no pain, no gain” applies here. For most knee rehabilitation contexts, this is not accurate and can set back progress. Fix: Use the general guideline of keeping exercise-related discomfort mild (often described as staying under about 3 to 4 out of 10) and ensure any discomfort settles within about an hour after exercise; stop and reassess if pain is sharp, severe, or persistent.
Mistake 5: Avoiding Exercise Entirely Out of Fear
On the opposite end, some people avoid movement altogether out of fear of making things worse, which, as discussed earlier, often leads to further deconditioning and can worsen pain over time. Fix: Start gently, following the modifications for significant current pain described above, and build confidence gradually through controlled, graded exposure to movement.
Mistake 6: Skipping the Hip-Focused Exercises
It is tempting to focus only on exercises that directly target the knee, overlooking exercises like clamshells and hamstring curls that address the hip and surrounding muscles. Fix: Remember that knee alignment and control are significantly influenced by hip strength; skipping these exercises leaves an important piece of the puzzle unaddressed.
Mistake 7: Not Adjusting Based on Your Body’s Feedback
Following a generic routine without paying attention to your own specific response, continuing to progress volume even when a particular exercise consistently causes more discomfort than others, for example, misses an opportunity to personalize your approach. Fix: Pay attention to which exercises feel best and which feel more provoking, and adjust volume or temporarily substitute alternatives accordingly, discussing persistent issues with a healthcare provider if needed.
Mistake 8: Expecting Overnight Results
As discussed earlier, meaningful improvement from a strengthening program typically takes several weeks of consistent effort. Expecting dramatic relief after a few days and giving up when that does not happen is one of the most common reasons people abandon otherwise effective exercise programs. Fix: Set expectations around a 6- to 8-week timeline, track your progress (see the tracking section later in this guide), and trust the process.
Exercises and Movements to Be Cautious With
Certain movements, while not inherently “bad,” are more likely to aggravate common knee issues and may be worth approaching cautiously, modifying, or avoiding until your knee is stronger and more comfortable, depending on your specific condition.
Deep Knee Bends and Full Squats
Deep squatting places significantly more compressive load on the kneecap and the joint itself compared with a partial squat or wall sit. For many people with kneecap-related pain (patellofemoral pain) in particular, deep squats can be provoking, at least initially. This does not mean squats should be avoided forever, graduated squat training is often part of a complete strengthening program, but starting with shallower ranges (as described in the wall sit instructions) and progressing depth gradually is generally a more comfortable approach for someone currently dealing with knee pain.
High-Impact Activities
Running, jumping, and other high-impact activities place substantially more force through the knee joint than walking or the strengthening exercises in this guide. If you are currently dealing with significant knee pain, it is often reasonable to temporarily reduce or pause high-impact activities while building a stronger foundation through the exercises in this guide, then gradually reintroduce them, ideally with guidance from a physical therapist, particularly if returning to running or sports is a goal.
Twisting Movements Under Load
Movements that combine knee bending with twisting, such as certain pivoting sports movements, can place unusual stress on the knee’s ligaments and meniscus, particularly if the surrounding muscles are not yet strong enough to control the movement well. This is less of a concern for controlled, planned exercise and more relevant to be aware of during sports or daily activities if you are in a vulnerable recovery period.
Prolonged Kneeling or Deep Flexion Positions
Activities that involve sustained deep knee bending, such as kneeling for extended periods (for example, gardening) or sitting in deep squatting positions, can be uncomfortable for some knee conditions, particularly those involving the kneecap or significant arthritis. Using a cushion when kneeling, taking breaks to change position, or using alternative tools (such as a long-handled gardening tool) can help reduce strain during these activities.
Stairs, Without Appropriate Preparation
While stair climbing itself is a normal, necessary activity rather than something to avoid, suddenly increasing stair volume (such as moving to a new multi-story home or taking on a job that requires significantly more stair climbing) without building adequate strength first can contribute to knee pain. The step-up exercise in this guide is specifically designed to help build the strength needed to handle stairs more comfortably over time.
A General Principle: Gradual Exposure, Not Permanent Avoidance
For most of the movements above, the goal is not permanent avoidance but rather gradual, controlled reintroduction as strength and comfort improve. Avoiding a movement entirely and indefinitely can sometimes contribute to ongoing sensitivity or fear around that movement, which is itself a recognized factor in some persistent pain conditions. Working with a physical therapist can be particularly valuable for safely and confidently reintroducing more demanding movements and activities over time.
Supporting Your Knees Beyond Exercise
Exercise is a central part of managing knee pain, but a few other factors commonly discussed alongside it are worth understanding.
Weight Management (Where Relevant)
For people who are carrying excess body weight, research consistently shows that even modest weight loss can meaningfully reduce the load placed on the knee joints during walking and other weight-bearing activities, which can translate into reduced pain, particularly for knee osteoarthritis. This is not relevant or appropriate advice for everyone, and is not a comment on any individual’s body size; it is simply a factor that research identifies as relevant to knee joint loading for those for whom it applies. If this is relevant to your situation, a conversation with a healthcare provider or registered dietitian can help you approach it in a way that fits your health and circumstances.
Footwear
Supportive, well-fitted shoes with adequate cushioning can influence how forces move through the knee during walking and standing. Worn-out shoes that have lost their cushioning and support, or shoes that are not well-suited to your foot shape or activity, can sometimes contribute to knee discomfort. If you have specific foot or gait concerns (such as significant flat feet or overpronation), a podiatrist or physical therapist can advise on whether specific footwear or orthotics might be helpful for your situation.
Surface and Terrain Awareness
Hard, uneven, or sloped surfaces can place different and sometimes greater demands on the knee compared with flat, even, cushioned surfaces. This does not mean avoiding varied terrain altogether, but being mindful of it, particularly during a period of significant pain, and choosing flatter or more cushioned walking routes when possible, can reduce unnecessary strain.
Rest and Activity Balance
Finding the right balance between staying active (which, as discussed, is generally beneficial) and allowing adequate recovery time, particularly after a more demanding activity or a flare-up, is a skill that develops with experience and attention to your body’s signals. Alternating between more and less demanding days, as outlined in the weekly schedule earlier in this guide, is one practical way to build in this balance.
Heat and Cold Therapy
Many people find that applying heat before exercise (such as a warm towel or heating pad for 10 to 15 minutes) helps loosen stiffness and makes movement more comfortable, while applying ice after exercise or during a flare-up (for 15 to 20 minutes) can help manage any resulting discomfort or mild swelling. These are general comfort measures with some supporting evidence for short-term symptom relief; they do not address the underlying cause of knee pain the way strengthening exercise does, but they can be a helpful complement.
Sleep and Overall Recovery
Adequate sleep supports general tissue recovery and can influence pain perception; poor sleep is associated with increased pain sensitivity in research across many types of chronic pain. While this is a broader health factor rather than a knee-specific intervention, it is worth considering as part of an overall approach to managing persistent pain.
When Bracing or Taping Might Help
Some people find a knee brace or taping technique helpful for additional support during specific activities, particularly during a flare-up or while building strength. This is often most appropriately guided by a physical therapist or doctor, who can recommend the type of support, if any, that fits your specific situation, since the “right” choice varies considerably depending on the underlying cause of knee pain.
Knee Pain Exercises for Specific Situations
While the core 7 exercises form a solid foundation for most common knee issues, here is guidance tailored to a few specific situations and populations.
Chair-Based Modifications for Limited Mobility or Balance Concerns
If getting down to and up from the floor is difficult, uncomfortable, or feels unsafe, several of the exercises can be adapted to a seated position.
Seated quad sets: Sit in a sturdy chair with your foot flat on the floor. Straighten one leg out in front of you, tighten the thigh muscle (as described in Exercise 1), hold, and relax. This works the same muscle as the floor-based version.
Seated straight leg raises (leg extensions): Sit in a sturdy chair. Slowly straighten one knee, lifting the foot until the leg is extended out in front of you, parallel to the floor if comfortable. Hold briefly, then lower with control. This directly replaces Exercise 2 for those who find lying on the floor difficult.
Seated marching (as a warm-up or gentle alternative): Sit in a chair and alternate lifting each knee toward your chest in a marching motion, which gently engages the hip flexors and quadriceps.
Chair-supported wall sits (modified): For Exercise 3, holding onto the back of a sturdy chair placed in front of you while performing a very shallow wall sit against a wall provides extra stability and confidence.
Standing hamstring curls with extra support: For Exercise 5, standing behind a chair and holding onto the back of it with both hands provides more stable support than holding a wall alone, which can be particularly helpful for those with balance concerns.
For Office Workers and People Who Sit Most of the Day
Prolonged sitting can contribute to muscle weakness and stiffness that may aggravate knee discomfort. Consider:
- Taking a short movement break every 30 to 60 minutes, even just standing up and doing 5 to 10 seated marches or a brief walk around the office.
- Performing seated quad sets or seated straight leg raises discreetly at your desk throughout the day, which can be done without anyone noticing and adds up to meaningful extra strengthening volume.
- Paying attention to desk and chair height, ensuring your knees are roughly level with or slightly below your hips when seated, which can reduce unnecessary strain during long sitting periods.
- Standing and gently bending and straightening the knees a few times before standing up from a long sitting period, rather than standing up abruptly after being still for a long time.
For Runners and Athletes
If knee pain is related to running or sports activity, this routine’s hip-focused exercises (clamshells and hamstring curls in particular) are often especially relevant, since hip weakness is strongly associated with running-related knee pain. Consider:
- Temporarily reducing running volume or intensity while building strength through this routine, rather than stopping entirely unless advised to do so by a healthcare provider.
- Gradually reintroducing running volume once strength improves, following a structured return-to-running approach, ideally with guidance from a physical therapist or running coach experienced in injury management.
- Paying attention to running surface, footwear age, and any recent changes in training volume, all of which are commonly discussed contributing factors to running-related knee pain.
For Older Adults Managing Arthritis-Related Stiffness
- Morning stiffness is common and often improves with gentle movement, so consider a very gentle warm-up (such as seated marching or ankle circles while still in bed or seated at the bedside) before getting up for the day.
- Heel slides (Exercise 7) are often particularly valuable for maintaining range of motion, and can be performed more frequently throughout the day if helpful.
- Consistency matters more than intensity; several short sessions throughout the day may feel more manageable and sustainable than one longer session.
- Water-based exercise (such as walking in a pool or water aerobics, where available) is often well-tolerated for arthritis-related knee pain, since water buoyancy reduces the load on the joints while still providing resistance for strengthening; this can be a valuable complement to the land-based exercises in this guide.
For Those Recovering From a Minor Injury (With Provider Clearance)
Once a healthcare provider has confirmed that controlled exercise is appropriate for your specific injury:
- Begin with the gentlest exercises (quad sets, heel slides) before progressing to the more dynamic options, following the general order presented in this guide, which roughly reflects a typical progression from gentle to more demanding.
- Progress more conservatively than the general guidelines suggest, since healing tissue may need more time before tolerating higher loads; your provider can give specific guidance on an appropriate timeline for your injury.
- Watch closely for any increase in swelling or sharp pain with each new exercise or progression, and report this to your provider if it occurs.
For Pregnant Individuals
Knee discomfort during pregnancy is relatively common, often related to changes in weight distribution, posture, and ligament laxity. Many of the gentler exercises in this guide (quad sets, heel slides, seated straight leg raises) are often well-tolerated, but it’s important to get individualized clearance and guidance from your obstetric care provider before starting or continuing any exercise program during pregnancy, since recommendations can vary based on your specific pregnancy and health status.
How to Track Your Progress
Tracking helps you notice gradual improvement that might otherwise be easy to miss day to day, and it helps you and any healthcare provider you work with understand what is actually happening over time.
What to Track
Pain levels: Rate your knee pain on a simple 0 to 10 scale (0 being no pain, 10 being the worst pain imaginable) at a consistent time, such as first thing in the morning or at the end of the day. Tracking this a few times a week, rather than obsessively multiple times a day, usually gives a clearer picture of the overall trend.
Function with specific activities: Note how specific, meaningful activities feel over time, such as climbing a flight of stairs, standing up from a low chair, or walking a certain distance. These functional markers are often more meaningful and motivating than the pain score alone.
Exercise consistency: A simple checkmark on a calendar or in a notes app for each day you complete your routine (full or quick version) helps you see your actual consistency, which is often better, or sometimes worse, than it feels in the moment.
Stiffness, especially morning stiffness: For arthritis-related knee pain in particular, note how long it takes for stiffness to ease up after waking or after a period of inactivity, since this is a commonly tracked marker of joint health.
Swelling: If swelling is part of your symptom picture, note whether it is present, and whether it is improving, stable, or worsening, since significant or worsening swelling is a signal to check in with a healthcare provider.
A Simple Weekly Tracking Template
| Week | Avg. pain (0–10) | Stairs | Standing from chair | Exercise days completed | Notes |
|---|---|---|---|---|---|
| 1 | |||||
| 2 | |||||
| 3 | |||||
| 4 |
Rate “stairs” and “standing from chair” on a simple scale of your choosing, such as easy, moderate difficulty, or hard, or a 0 to 10 difficulty scale, whichever feels more intuitive to you.
Reviewing Your Progress Every 2 to 4 Weeks
Set a reminder to review your tracking every couple of weeks. Ask yourself:
- Is my average pain level trending down, staying the same, or trending up?
- Are specific activities (stairs, standing, walking) feeling easier over time?
- Have I been consistent with the exercise routine, and if not, what got in the way?
- Do I need to progress any exercises (more reps, added resistance) based on how comfortable the current level feels?
When Tracking Suggests You Should See a Professional
If, after 3 to 4 weeks of consistent, appropriate exercise, your tracking shows no improvement, or shows a worsening trend, this is useful, specific information to bring to a doctor or physical therapist. Rather than simply saying “my knee still hurts,” you can share concrete details: which exercises you have been doing, how consistently, and how your pain and function have trended, which helps a healthcare provider assess your situation more effectively.
Troubleshooting: What to Do If Exercises Hurt
It’s common to encounter some bumps along the way. Here is how to think through a few common scenarios.
“An Exercise Causes Sharp Pain“
Stop that specific exercise. Sharp, sudden, or significantly worse pain during an exercise, as opposed to the mild, dull discomfort of muscle effort, is a signal that something about the movement, the range of motion, the load, or the specific exercise itself, is not currently appropriate for your knee. Try a gentler variation (such as a smaller range of motion) if one is suggested for that exercise, or substitute a gentler exercise from this guide (such as returning to quad sets and heel slides) while the sharper pain settles. If sharp pain persists or recurs across multiple exercises, check in with a healthcare provider.
“My Knee Feels Worse the Day After Exercise”
Some mild, dull soreness the day after starting a new exercise or increasing volume is common and often resembles typical muscle soreness from any new physical activity. If this mild soreness settles within a day or two and does not worsen with continued, appropriately-dosed exercise, it is often a normal part of the adaptation process. If the “worse” feeling involves sharp pain, significant swelling, or a level of discomfort that interferes with normal daily activities, scale back the volume or intensity of your most recent session and allow more recovery time before trying again, and consider whether you progressed too quickly.
“One Exercise Feels Fine, But Another Consistently Bothers Me”
This is valuable, specific information. Temporarily reduce or pause the specific exercise that is provoking discomfort, while continuing with the others that feel comfortable. Over time, you can attempt to gently reintroduce the provoking exercise at a lower volume or modified range of motion, paying close attention to how it feels. If one particular movement pattern consistently causes trouble, this is worth discussing with a physical therapist, who may be able to identify why that specific movement is problematic for your knee and offer a tailored modification.
“I Don’t Feel Anything, Is It Working?”
Especially with the gentler exercises like quad sets, some people feel they are not “doing enough” if the exercise does not feel particularly challenging. This is often appropriate, especially in early stages, since these exercises are intentionally gentle. If an exercise consistently feels too easy over 1 to 2 weeks, use the progression suggestions provided for each exercise (increased reps, added resistance, increased hold time) to appropriately increase the challenge.
“My Pain Comes and Goes Unpredictably”
Fluctuating pain is common with many chronic knee conditions and does not necessarily mean your exercise routine is ineffective or that something is going wrong. Factors like activity levels on a given day, weather changes (commonly reported by people with arthritis, though the research on this connection is mixed), sleep, stress, and simple day-to-day variation can all influence how a joint feels. Continue tracking over a longer period (several weeks) to identify the overall trend, rather than reacting strongly to single days.
“I’m Not Sure If I’m Doing the Exercises Correctly”
If possible, recording yourself performing an exercise on your phone and comparing it to the step-by-step instructions in this guide can help identify form issues. Performing exercises in front of a mirror can serve a similar purpose for exercises like wall sits and step-ups, where knee alignment is particularly important to monitor. If you remain unsure, even a single consultation with a physical therapist to check your form on these specific exercises can be valuable and is often covered, at least partially, by health insurance in many places.
“I Had to Stop for a While, How Do I Restart?”
Whether due to illness, a busy period, or a temporary flare-up, restart at a lower volume than where you left off, roughly 50 to 75 percent of your previous level if you were away for more than two weeks, and build back up over 1 to 2 weeks rather than immediately returning to your previous volume, which can increase the risk of excessive soreness or a setback.
Understanding Your Knee: A Quick Anatomy Primer
A basic understanding of how the knee is built can make it easier to understand why these particular exercises are recommended, and why certain movements or positions feel the way they do.
The Main Structures
Bones: The knee joint is formed where three bones meet: the femur (thigh bone), the tibia (shin bone), and the patella (kneecap), which sits in a groove at the front of the femur.
Cartilage: A layer of smooth cartilage covers the ends of the femur and tibia, allowing them to glide against each other with minimal friction. This is the tissue that gradually wears down in osteoarthritis.
Meniscus: Two C-shaped pieces of tougher cartilage (the medial and lateral meniscus) sit between the femur and tibia, acting as shock absorbers and helping distribute weight evenly across the joint.
Ligaments: Several ligaments stabilize the knee, including the anterior and posterior cruciate ligaments (ACL and PCL) inside the joint, and the medial and lateral collateral ligaments (MCL and LCL) on the sides, which control how much the joint can move in different directions and prevent excessive, unstable movement.
Tendons: The quadriceps tendon connects the quadriceps muscle to the top of the kneecap, and the patellar tendon connects the bottom of the kneecap to the shin bone; together, these transmit the force generated by the quadriceps muscle to straighten the knee.
Muscles: As discussed throughout this guide, the quadriceps (front of the thigh), hamstrings (back of the thigh), and the muscles of the hip, particularly the gluteus medius, all play significant roles in supporting and controlling the knee joint during movement.
How These Structures Relate to Common Pain Patterns
- Pain at the front of the knee, around or behind the kneecap, is often related to how the kneecap tracks within its groove, which is influenced significantly by quadriceps and hip strength and alignment, which is why patellofemoral pain responds well to the strengthening approach in this guide.
- Pain along the inside or outside joint line can sometimes relate to the meniscus or collateral ligaments, and while general strengthening remains valuable, this pattern is more often worth a professional evaluation to understand the specific structures involved, particularly if there was a specific injury event.
- Generalized stiffness and aching, often worse in the morning or after rest, is a common pattern associated with osteoarthritis and general joint stiffness, which the full routine, particularly the range-of-motion-focused heel slides, is designed to address.
- Pain along the outside of the knee, particularly during repetitive activities like running, is a classic pattern associated with IT band syndrome, which is why hip-focused strengthening (clamshells in particular) is emphasized.
Why “Strengthening the Muscles Around the Joint” Is Such a Common Theme
Because the knee joint itself has limited ability to actively protect itself, and because so many common sources of knee pain relate to how well the surrounding muscles control movement and absorb force, strengthening those muscles is one of the most consistently supported, broadly applicable interventions across many different underlying causes of knee pain. This is part of why the same core group of exercises, quad, hamstring, and hip strengthening, along with range of motion work, appears again and again across physical therapy guidelines for a wide range of knee conditions.
A Closer Look at Knee Osteoarthritis and Exercise
Because knee osteoarthritis is among the most common causes of chronic knee pain, particularly in adults over 50, it deserves a more detailed look.
What Happens in Osteoarthritis
Osteoarthritis involves the gradual breakdown of the cartilage that cushions the ends of the bones within the joint. As cartilage thins, bones can come into closer contact, and the joint may develop small bony growths called osteophytes, along with mild inflammation. Common symptoms include pain with activity, stiffness (particularly after rest or in the morning, typically lasting less than 30 minutes with osteoarthritis, as opposed to longer morning stiffness, which can be more suggestive of inflammatory arthritis types), and sometimes mild swelling.
Why Exercise Is a Core Recommended Treatment
Major clinical guidelines for knee osteoarthritis, including those from organizations such as the American College of Rheumatology and the Osteoarthritis Research Society International, consistently list exercise therapy, particularly strengthening exercise, as a first-line, strongly recommended treatment. This is not simply “something that can’t hurt”; it is backed by numerous randomized controlled trials showing meaningful reductions in pain and improvements in function.
How Exercise Helps Specifically With Osteoarthritis
- Reduces joint loading by improving the muscles’ ability to absorb and control force, reducing the direct load on the already-compromised cartilage.
- Improves joint lubrication and nutrient exchange within the cartilage, which, unlike most tissues, does not have its own direct blood supply and relies partly on the movement of joint fluid (which occurs with joint movement) to receive nutrients and remove waste products.
- Maintains and improves range of motion, counteracting the stiffness that often develops with reduced activity.
- Supports healthy body weight when combined with appropriate nutrition, which, as discussed earlier, can meaningfully reduce joint loading for those for whom this is relevant.
- May have a mild anti-inflammatory effect over time, as suggested by some research on regular, moderate exercise and systemic inflammation markers, though this effect is generally modest and is just one of several ways exercise is thought to help.
Realistic Expectations for Osteoarthritis-Related Pain
Exercise therapy for osteoarthritis is generally understood as a management strategy that improves pain and function, rather than a cure that reverses the underlying joint changes, since currently, cartilage damage from osteoarthritis is not reversible through exercise or most other currently available treatments. That said, many people experience significant, meaningful improvement in their day-to-day pain and ability to perform activities through consistent exercise, even though the underlying joint changes remain present on imaging.
When Osteoarthritis Needs More Than Exercise
For some people, particularly with more advanced osteoarthritis, exercise alone may not be sufficient to manage symptoms to a satisfactory degree, and additional treatments, ranging from pain management strategies to injections to, in some cases, surgical options like joint replacement, may be appropriate. These decisions are made together with an orthopedic provider based on the severity of symptoms, imaging findings, and how much the condition is affecting quality of life. Exercise remains a recommended component of management even for those pursuing these additional treatments, both before and after, where applicable (such as “prehabilitation” before a planned knee replacement, which research suggests can improve post-surgical outcomes).
Common Myths About Knee Pain, Debunked
Myth 1: “If Your Knee Hurts, You Should Stop Moving It”
Reality: As discussed throughout this guide, for most common, non-acute causes of knee pain, appropriate movement and strengthening are more effective than prolonged rest, which often leads to further deconditioning and, paradoxically, more pain over time. Acute, significant injuries are an exception where initial rest and medical evaluation are appropriate.
Myth 2: “Cracking or Popping Sounds Mean Something Is Wrong”
Reality: Joint sounds, sometimes called crepitus, are extremely common and, on their own, without accompanying pain, swelling, or other symptoms, are generally not considered a sign of a problem. Many people have noisy, symptom-free knees throughout their lives. If joint sounds are accompanied by pain, swelling, or a sensation of catching or locking, that combination is worth mentioning to a healthcare provider, but the sound alone is not typically a cause for concern.
Myth 3: “Running Destroys Your Knees”
Reality: Despite this being a widely held belief, a substantial body of research has not found that recreational running increases the risk of knee osteoarthritis in the general population; some research even suggests recreational runners may have a lower risk of knee osteoarthritis compared with sedentary individuals, possibly related to the general health and strength benefits of regular exercise. Extremely high-volume, long-term competitive running, or running with significant pre-existing joint instability or injury, may carry different risk considerations, but moderate recreational running is not well-supported as a cause of knee damage in otherwise healthy knees.
Myth 4: “You Need Expensive Equipment or a Gym Membership to Strengthen Your Knees”
Reality: As this guide demonstrates, all seven core exercises can be performed at home with minimal or no equipment, using just body weight, a wall, and a sturdy chair. While gym equipment and resistance bands can be useful progression tools, they are not required to build meaningful strength.
Myth 5: “Once You Have Knee Pain, It Will Only Get Worse Over Time”
Reality: While some underlying conditions, such as osteoarthritis, do involve gradual changes over time, pain and function do not necessarily follow the same trajectory as the underlying joint changes, and many people experience significant, lasting improvement in their symptoms and daily function through consistent exercise and appropriate management, even when some degree of underlying joint change remains present.
Myth 6: “Stretching Alone Will Fix Knee Pain”
Reality: While gentle stretching, as included in the cool-down routine in this guide, has a role in supporting flexibility and comfort, the strongest evidence for improving knee pain and function points to strengthening exercise as the more central intervention. Stretching alone, without addressing muscle strength, is generally not sufficient for most common causes of knee pain.
Myth 7: “Glucosamine and Chondroitin Supplements Will Fix the Problem”
Reality: Research on glucosamine and chondroitin supplements for knee osteoarthritis has produced mixed and generally unconvincing results, with many well-designed studies failing to show a clear, meaningful benefit beyond placebo for most people. Some individuals report subjective improvement, and these supplements are generally considered low-risk for most people, but they should not be relied upon as a primary treatment in place of exercise, which has much stronger supporting evidence. If you are considering any supplement, it is worth discussing with your doctor, particularly regarding interactions with other medications.
Myth 8: “You Should Avoid All Weight-Bearing Exercise If You Have Knee Pain”
Reality: With appropriate selection and progression, as outlined throughout this guide, weight-bearing exercises like wall sits and step-ups are not only generally safe for most common causes of knee pain but are specifically valuable because they train the muscles in positions that closely mirror real daily activities like standing, walking, and climbing stairs.
Myth 9: “A Brace Will Fix the Underlying Problem”
Reality: A knee brace can provide helpful additional support and comfort during certain activities, particularly during a flare-up, but it does not address the underlying muscle weakness or joint changes contributing to the pain. Braces are generally best thought of as a complementary comfort and support tool, used alongside, not instead of, an appropriate strengthening program.
Myth 10: “Age Is the Only Factor, So There’s Nothing You Can Do”
Reality: While age is a relevant factor for some causes of knee pain, particularly osteoarthritis, research consistently shows that people of all ages, including older adults, experience meaningful benefit from appropriate strengthening exercise. Age alone does not mean exercise will not help; it simply means the starting point, progression pace, and specific modifications may look different than they would for a younger person.
Nutrition and Lifestyle Factors Often Discussed Alongside Knee Health
While this guide centers on exercise, a few broader lifestyle factors are commonly discussed in relation to joint health and are worth briefly understanding.
Anti-Inflammatory Eating Patterns
Some research has explored whether dietary patterns rich in fruits, vegetables, whole grains, fish (or, for a plant-based approach, omega-3-rich foods like flaxseed and walnuts), and healthy fats, and lower in highly processed foods and added sugar, may be associated with lower levels of systemic inflammation, which some researchers theorize could play a role in certain types of joint pain, particularly inflammatory arthritis types. The evidence specifically linking diet to osteoarthritis symptoms is less robust than for inflammatory arthritis, but a generally nutrient-dense, whole-food-focused eating pattern is well-supported for overall health regardless of its specific effect on joint pain.
Hydration
Adequate hydration supports overall tissue health, including the cartilage within joints, which has a high water content. While dehydration is not typically identified as a direct cause of knee pain, maintaining good hydration habits is a reasonable, low-risk part of a general health-supportive routine.
Vitamin D and Bone Health
Vitamin D plays an important role in bone health, and some research has explored potential links between vitamin D status and joint health, though findings specifically related to osteoarthritis symptoms have been mixed. If you have concerns about your vitamin D levels, this is a reasonable topic to discuss with your doctor, who can advise on testing and supplementation if appropriate for your individual situation.
Smoking and Joint Health
Smoking is associated with various negative effects on tissue healing and is generally considered unfavorable for musculoskeletal health, including some research suggesting associations with worse outcomes for certain joint conditions. If you smoke and are looking for additional reasons to consider quitting, supporting joint and overall tissue health is one of many potential benefits, though this is a broader health topic beyond the scope of this exercise-focused guide.
Stress Management
As mentioned earlier, stress and pain are known to interact, with higher stress levels associated with increased pain sensitivity in research across many pain conditions. Approaches like regular physical activity (including the exercises in this guide), adequate sleep, and stress-reduction practices that work for you can be a reasonable part of a holistic approach to managing persistent pain, alongside, not instead of, the direct, targeted strengthening approach that is this guide’s primary focus.
How This Compares to Other Common Knee Pain Treatments
Understanding where exercise fits among other common treatment approaches can help you have more informed conversations with your healthcare provider and set realistic expectations.
Exercise Therapy vs. Pain Medication
Over-the-counter and prescription pain medications can provide valuable short-term symptom relief and may make it more comfortable to engage in exercise, particularly during a flare-up. However, medication does not address the underlying muscle weakness or joint mechanics that often contribute to ongoing knee pain, and some research directly comparing structured exercise programs to medication for knee osteoarthritis has found comparable or sometimes superior pain relief with exercise, without the potential side effects associated with long-term medication use. Many healthcare providers recommend using both together, medication for symptom management as needed, and exercise as the more foundational, longer-term strategy, rather than viewing them as competing options.
Exercise Therapy vs. Injections
Corticosteroid injections can provide temporary relief of inflammation and pain, particularly during a significant flare-up, though effects are generally short-term (weeks to a few months) and repeated use is generally limited due to potential effects on cartilage with frequent, long-term use. Other injection types, such as hyaluronic acid (viscosupplementation) or platelet-rich plasma (PRP), have more mixed and still-developing evidence bases. Injections are generally considered a complementary or bridging treatment, sometimes used to provide enough symptom relief to more comfortably engage in an exercise program, rather than a replacement for the longer-term benefits of strengthening exercise.
Exercise Therapy vs. Surgery
For most common, non-severe causes of knee pain, including mild to moderate osteoarthritis and conditions like patellofemoral pain, a trial of structured exercise therapy is generally recommended before considering surgical options, and many people achieve sufficient symptom relief through exercise alone, avoiding the need for surgery. For more severe cases, particularly advanced osteoarthritis significantly limiting quality of life, or certain structural injuries (such as some ligament or meniscus tears), surgery may become an appropriate consideration after conservative treatments, including exercise, have been tried, or in some cases of acute injury, more urgently. This decision is made individually with an orthopedic specialist based on the specific diagnosis, severity, and how much the condition affects your life. Notably, exercise before surgery (“prehabilitation”) and after surgery (post-operative rehabilitation) remains an important part of the process even when surgery is pursued.
Exercise Therapy vs. Passive Treatments (Massage, Ultrasound, Electrical Stimulation)
Passive treatments, meaning treatments done to you rather than active participation on your part, can offer short-term comfort and may be a reasonable complement, particularly in early stages or during a flare-up, but research generally shows that active exercise therapy produces more significant and lasting improvements in pain and function compared with passive treatments alone. Many physical therapy approaches combine some passive treatment in early visits with a progressively greater emphasis on active, exercise-based rehabilitation as the primary driver of long-term improvement.
Where Physical Therapy Fits In
A physical therapist can provide a combination of professional assessment, hands-on treatment where appropriate, individually tailored exercise prescription (which may differ from this general guide based on your specific findings), and guided progression over time, along with accountability and expert troubleshooting if an exercise is not going well. For many people, especially those with more complex or persistent symptoms, working with a physical therapist, even for just a handful of initial visits to establish a personalized program, offers significant value beyond what a general guide like this one can provide.
Building a Knee-Friendly Exercise Toolkit
While the 7 core exercises in this guide require minimal equipment, a few inexpensive items can support your progress as you advance.
Resistance Bands
Light to medium resistance loop bands (sometimes called mini bands) are inexpensive, portable, and useful for adding resistance to exercises like clamshells and hamstring curls once the basic bodyweight version becomes comfortable. Starting with a lighter resistance band and progressing to a heavier one over time, rather than starting too challenging, generally produces a smoother, more sustainable progression.
Ankle Weights
Adjustable ankle weights (typically starting around 1 to 5 pounds / 0.5 to 2.3 kg) are useful for adding resistance to straight leg raises as that exercise becomes easier with just body weight. Starting with the lightest available weight and progressing gradually is generally recommended, since adding too much resistance too quickly can increase strain before the muscles are adequately prepared.
A Yoga Mat or Exercise Mat
A supportive, cushioned surface makes floor-based exercises like straight leg raises, clamshells, and heel slides more comfortable, particularly for those with sensitive knees, hips, or lower backs when lying on a hard floor.
A Sturdy, Stable Chair
As referenced throughout this guide, a sturdy chair without wheels provides valuable support for balance during standing exercises and serves as the basis for several chair-based modifications. Avoid chairs with wheels or unstable, lightweight chairs for exercises requiring balance support.
A Low Step or Step Platform
For the step-up exercise, a stable, low step (such as a sturdy step stool, a low exercise step platform, or the bottom stair of a staircase with a secure railing nearby) is needed. Adjustable step platforms, commonly available and inexpensive, allow you to gradually increase step height as you progress.
None of This Is Required to Begin
It bears repeating: every one of the 7 core exercises can be performed without any of the equipment described above. These items are optional tools for progression and added comfort, not prerequisites for getting started.
A 4-Week Sample Progression Plan
For those who want a more structured starting framework, here is a sample 4-week progression that gradually builds volume and, where appropriate, introduces light resistance. Adjust the pace based on your own comfort and response; this is a template, not a rigid prescription.
Week 1: Foundation
- Focus: Learning correct form and establishing the daily habit.
- Quad sets: 10 reps, 5-second holds, 2x/day
- Straight leg raises: 1 set of 10 per leg, daily
- Heel slides: 10 reps per leg, daily
- Clamshells: 1 set of 10 per side, 3 to 4 days this week
- Wall sits: 3 holds of 10 seconds, 3 to 4 days this week
- Step-ups and hamstring curls: introduce lightly, 1 set of 6 to 8, only if comfortable; otherwise, hold off until week 2.
Week 2: Building Consistency
- Quad sets: 10 reps, 5 to 8-second holds, 2x/day
- Straight leg raises: 2 sets of 10 per leg, 4 to 5 days this week
- Heel slides: 10 to 12 reps per leg, daily
- Clamshells: 2 sets of 10 to 12 per side, 4 to 5 days this week
- Wall sits: 4 holds of 10 to 15 seconds, 4 to 5 days this week
- Step-ups: 1 to 2 sets of 8 per leg, 3 days this week
- Hamstring curls: 1 to 2 sets of 8 to 10 per leg, 3 days this week
Week 3: Full Routine
- Begin performing the full routine (all 7 exercises at the standard starting volume described earlier in this guide) on 3 to 4 days this week, with the quick routine on remaining days.
- If all exercises feel comfortable and controlled, consider modest progressions, such as a slightly deeper wall sit or a slightly higher step for step-ups.
Week 4: Progression
- Continue the full routine 3 to 5 days this week.
- Begin introducing light resistance where appropriate and if the bodyweight version feels well-controlled: a light ankle weight for straight leg raises, or a light resistance band for clamshells and hamstring curls.
- Reassess your tracking notes from the past 4 weeks (see the tracking section) and adjust your ongoing routine based on what you are noticing.
Beyond Week 4
By this point, many people have a good sense of their baseline routine and appropriate progression pace. Continue the weekly schedule outlined earlier in this guide, progressing individual exercises gradually over the following weeks and months as strength improves, and revisiting the modification guidance if you experience a flare-up or need to adjust volume at any point.
Signs Your Routine Is Working
Beyond pain scores, these are the broader indicators that your strengthening routine is having a meaningful effect:
- Stairs feel more manageable, particularly going down stairs, which places significant demand on the quadriceps.
- Standing up from a low chair or the floor requires less effort or less reliance on pushing off with your arms.
- You can walk longer distances before noticing significant discomfort.
- Morning stiffness resolves more quickly than it used to.
- You feel more confident and less fearful about using your knee during daily activities.
- You notice the exercises themselves feel easier at the same volume, a sign it may be time to progress.
- You experience fewer unpredictable flare-ups, or flare-ups that do occur feel less severe or resolve more quickly.
- You find yourself naturally moving more throughout the day, taking stairs instead of avoiding them, for example, simply because your knee feels more capable.
Not every sign needs to be present for your routine to be working; even one or two of these improving over several weeks is a meaningful, positive sign worth continuing to build on.
Frequently Asked Questions About Knee Pain Exercises
How often should I do these knee pain exercises?
For most people, performing the full routine 3 to 5 days per week, with a shorter “quick routine” on the remaining days, provides a good balance of consistent stimulus and adequate recovery. Some of the gentlest exercises, such as quad sets, are often recommended multiple times per day, even daily, since they involve minimal joint stress.
Can I do these exercises every single day?
Yes, for most people, this routine, particularly at moderate volumes, is gentle enough to perform daily without issue, and daily or near-daily movement is often beneficial for knee pain, as discussed throughout this guide. Pay attention to your body’s response; if you notice increasing fatigue or discomfort with daily practice, incorporating 1 to 2 lighter or rest days per week, as outlined in the sample weekly schedule, is a reasonable adjustment.
How long until I notice improvement?
Most research on structured exercise programs for knee pain shows meaningful improvement within 6 to 8 weeks of consistent practice, with some people noticing initial changes, such as reduced stiffness, within 2 to 3 weeks. Individual timelines vary considerably based on the underlying cause of pain, consistency, and other individual factors.
Is it normal for my knees to feel sore after starting this routine?
Mild, dull soreness, similar to typical muscle soreness after starting any new exercise, is common in the first 1 to 2 weeks and generally improves as your body adapts. This differs from sharp, severe, or worsening pain, which is a signal to scale back and reassess, as discussed in the troubleshooting section of this guide.
Can I do these exercises if I have knee arthritis?
Yes. Strengthening exercise, including the types of exercises in this guide, is a core, strongly recommended treatment for knee osteoarthritis according to major clinical guidelines, as discussed in detail earlier in this article. Start conservatively, pay attention to your body’s response, and consider the modifications suggested for significant current pain if you are currently experiencing a flare-up.
Should I exercise through pain, or only when pain-free?
Neither extreme is typically recommended. Completely avoiding exercise until pain is entirely gone often leads to further deconditioning, while pushing through significant, sharp pain can be counterproductive or, in some cases, risky. The general guideline used by many physical therapists is to allow mild discomfort (often described as staying under about 3 to 4 out of 10) that settles down within about an hour after exercise, while avoiding sharp, severe, or worsening pain.
Can these exercises help with knee pain from running?
Yes, particularly the hip-focused exercises like clamshells, since hip weakness is strongly associated with common running-related knee pain patterns like patellofemoral pain and IT band syndrome. Combining this strengthening routine with appropriate adjustments to running volume, as discussed in the “Knee Pain Exercises for Specific Situations” section, is a commonly recommended approach.
Do I need to see a doctor before starting these exercises?
For general, non-severe, ongoing knee pain without the warning signs described earlier in this guide (recent significant injury, inability to bear weight, significant swelling, locking, numbness, or signs of infection), it is generally reasonable to try this type of gentle, gradual exercise approach. If you have any of those warning signs, a recent specific injury, or significant uncertainty about your specific situation, seeing a doctor or physical therapist first is recommended.
Can these exercises make my knee pain worse?
If performed with appropriate progression, attention to form, and responsiveness to pain signals (as outlined throughout this guide), these exercises are generally well-tolerated and are specifically designed around approaches commonly used in physical therapy for various knee conditions. That said, any individual exercise can occasionally aggravate a specific condition for a specific person, which is why the troubleshooting section and the modification guidance for different situations are provided; adjusting or substituting a specific exercise that consistently causes trouble for you is a reasonable response.
What if only one knee hurts, do I still exercise both?
Yes, in most cases, exercising both legs is recommended, even if pain is isolated to one side, for the reasons discussed in the “daily and weekly routine” section: maintaining overall strength and balance, and often addressing some degree of weakness that may be present, even subtly, on the “good” side as well.
Can I combine this routine with walking or other cardio exercise?
Yes, and this is generally encouraged. Walking, in particular, is a well-supported, low-impact activity for most people with knee pain, and combining regular walking with this targeted strengthening routine is a commonly recommended, complementary approach. If a specific cardio activity consistently increases your knee pain, this is worth discussing with a healthcare provider, who may suggest modifications to the activity or type of cardio exercise.
How much weight or resistance should I eventually work up to?
There is no single universal target, since appropriate resistance depends on your starting strength, goals, and how your body responds. The general principle is gradual, consistent progression: once a given volume and resistance level feels comfortably manageable for 1 to 2 weeks, it is generally reasonable to progress slightly, whether through added repetitions, added resistance, or increased hold times, as outlined in the progression notes for each exercise.
Can children or teenagers do these exercises?
This guide is primarily written with adults in mind. Knee pain in children and teenagers can have different underlying causes (such as growth-related conditions) compared with adults, and it’s advisable to have a pediatrician or pediatric physical therapist evaluate knee pain in a child or teenager before starting a structured exercise program.
Is it okay to use ice or heat alongside these exercises?
Yes, many people find heat helpful before exercise to loosen stiffness, and ice helpful after exercise or during a flare-up to manage discomfort, as discussed in the “Supporting Your Knees Beyond Exercise” section. These are general comfort measures that can reasonably be combined with this exercise routine.
What’s the difference between this routine and general leg day exercises at the gym?
While there is some overlap (both involve strengthening the quadriceps, hamstrings, and glutes), this routine is specifically selected and dosed based on physical therapy research for knee pain rehabilitation, emphasizing controlled, joint-friendly movement patterns, appropriate starting volumes, and a gradual progression designed for someone managing knee discomfort, rather than general fitness or muscle-building goals, which often involve heavier loads and different exercise selections that may not be appropriate as a starting point for an irritated or painful knee.
Can I do these exercises if I’ve had a total knee replacement?
If you have had a knee replacement, you should follow the specific post-surgical rehabilitation protocol provided by your surgeon and physical therapy team, which is carefully timed and individualized to your surgery and recovery. Some of the general exercise types in this guide (such as quad sets and heel slides) are commonly part of standard post-knee-replacement rehabilitation protocols, but timing, progression, and any restrictions should be directed by your surgical and rehabilitation team, not this general guide.
Will these exercises help bone-on-bone knee arthritis?
Even in cases described as “bone-on-bone” (a colloquial term often used to describe advanced osteoarthritis with significant cartilage loss visible on imaging), strengthening exercise remains a recommended component of management in clinical guidelines, since it can still meaningfully improve pain and function by improving how well the surrounding muscles support and control the joint, even though it cannot restore lost cartilage. Many people with advanced osteoarthritis experience meaningful benefit from exercise, sometimes sufficient to delay or avoid surgery, though for some, exercise alone may not be enough and additional treatment options, including surgery, may eventually become appropriate; this is a conversation to have with an orthopedic provider based on your specific situation and imaging.
How do I know if I should progress an exercise or keep it at the same level?
A reasonable general guideline: if a given volume of an exercise has felt comfortable and well-controlled (without significant soreness or pain) for about 1 to 2 weeks, it is generally reasonable to progress, using the specific progression option suggested for that exercise. If you are still experiencing some discomfort or are still working on controlling the movement well, it’s generally better to stay at the current level a bit longer before progressing.
Are there exercises I should avoid completely if I have knee pain?
Rather than a universal list of exercises to avoid entirely (since the right answer depends heavily on your specific condition), the “Exercises and Movements to Be Cautious With” section of this guide covers general categories, deep squats, high-impact activities, twisting under load, and prolonged deep flexion, worth approaching thoughtfully and progressively rather than avoiding forever or diving into without preparation.
Can massage help alongside these exercises?
Massage, whether self-massage with a foam roller or professional massage therapy, can be a reasonable complementary comfort measure for some people, particularly for muscle tightness around the knee and hip. It is generally considered a complement to, rather than a replacement for, active strengthening exercise, which has stronger evidence for addressing the underlying contributors to most common knee pain.
What should I wear or bring for this routine?
Comfortable clothing that allows full movement at the hip and knee, supportive athletic shoes (or a stable bare-foot surface for floor-based exercises), a mat for comfort on the floor, and access to a wall and sturdy chair cover everything needed for this routine, as described in the preparation section earlier in this guide.
A Closer Look at Patellofemoral Pain Syndrome
Since this is one of the most common causes of knee pain in younger, active adults, it is worth understanding in a bit more detail.
What It Is
Patellofemoral pain syndrome refers to pain in and around the kneecap (patella), often described as a dull ache that worsens with activities that load the front of the knee: squatting, kneeling, climbing or descending stairs, and prolonged sitting with the knees bent (sometimes called “theater sign,” since it classically worsens during long periods sitting at a movie theater or similar).
What Contributes to It
Research has identified several commonly associated factors, including weakness of the quadriceps (particularly the inner portion, called the vastus medialis), weakness of the hip muscles (particularly the gluteus medius and other hip external rotators), which can allow the thigh to rotate inward during activity and alter how the kneecap tracks in its groove, and sometimes tightness in surrounding structures like the IT band or hamstrings.
Why the Exercises in This Guide Are Relevant
The combination of quadriceps strengthening (quad sets, straight leg raises, wall sits, step-ups) and hip strengthening (clamshells, and the hip stabilization demanded by step-ups and wall sits) directly targets the muscle groups most consistently identified in research as being weak or under-engaged in people with patellofemoral pain. Multiple clinical trials have found that combined hip and knee strengthening programs produce better outcomes for patellofemoral pain than knee-focused exercise alone, which is part of why this guide deliberately includes both.
A Practical Note on Progression
For patellofemoral pain specifically, many people find that exercises involving a greater degree of knee bending (such as deeper wall sits or deeper step-ups) are more likely to provoke discomfort than exercises performed with the knee closer to straight (such as straight leg raises or shallow wall sits). If this applies to you, starting with the straighter-knee versions of each exercise and very gradually increasing the range of knee bending as symptoms allow is a reasonable, commonly used approach.
A Closer Look at IT Band Syndrome
What It Is
Iliotibial (IT) band syndrome causes pain along the outside of the knee, typically appearing or worsening during repetitive activities like running, cycling, or hiking, particularly on downhill terrain. It is caused by irritation where the IT band, a thick band of connective tissue running from the hip to just below the outer knee, passes over a bony prominence on the outside of the knee.
What Contributes to It
Weakness in the gluteus medius, the same hip muscle targeted by the clamshell exercise in this guide, is one of the most consistently identified contributing factors in research on IT band syndrome, since this muscle helps control hip and thigh alignment during repetitive activities like running; when it is weak, compensatory movement patterns can increase strain on the IT band. Sudden increases in training volume, worn-out footwear, and running on cambered or consistently sloped surfaces are also commonly discussed contributing factors.
Why Hip Strengthening Is Central to Treatment
Research on IT band syndrome treatment consistently identifies hip abductor strengthening (targeting the gluteus medius) as a key, evidence-supported component of rehabilitation, often more emphasized than direct stretching or treatment of the IT band itself, which is a thick, relatively inelastic structure that does not lengthen significantly even with dedicated stretching. This is why the clamshell exercise in this guide is relevant not just for general knee support but specifically for IT band-related pain.
Additional Considerations
For IT band syndrome related to running or cycling, temporarily reducing training volume, checking footwear age (running shoes are often recommended for replacement every 300 to 500 miles, depending on the shoe and runner, though this varies), and gradually reintroducing volume as strength improves and symptoms allow are commonly recommended complementary strategies alongside the strengthening exercises in this guide.
Glossary: Key Terms Used in This Guide
Isometric exercise: A type of exercise where the muscle contracts without the joint moving through a range of motion, such as the quad set exercise in this guide. Often used as a gentle starting point in rehabilitation.
Patellofemoral: Relating to the kneecap (patella) and its relationship with the groove in the femur (thigh bone) that it glides within during knee movement.
Quadriceps: The group of four muscles on the front of the thigh responsible for straightening the knee; one of the primary muscle groups targeted throughout this guide.
Hamstrings: The group of muscles on the back of the thigh responsible for bending the knee and extending the hip; works in balance with the quadriceps to stabilize the knee.
Gluteus medius: A hip muscle on the outer side of the hip that plays a key role in controlling thigh and knee alignment during walking and single-leg activities; a frequent focus of knee rehabilitation programs due to its influence on knee alignment.
Range of motion: The full extent of movement available at a joint, in this case, how far the knee can bend and straighten.
Meniscus: C-shaped cartilage structures within the knee joint that act as shock absorbers between the thigh bone and shin bone.
Osteoarthritis: A joint condition involving the gradual breakdown of cartilage, commonly affecting the knee, and a frequent cause of chronic knee pain, particularly in older adults.
IT band (iliotibial band): A thick band of connective tissue running along the outside of the thigh from the hip to just below the knee; a common source of knee pain, particularly in runners, when irritated.
Crepitus: Popping, cracking, or grinding sounds or sensations in a joint, which are common and, without accompanying pain or other symptoms, are generally not considered concerning on their own.
Prehabilitation (“prehab”): Exercise performed before a planned surgery (such as a knee replacement) with the goal of improving strength and function going into the procedure, which research suggests can improve post-surgical recovery outcomes.
Deconditioning: A decline in physical fitness and muscle strength due to reduced activity, which can occur as a secondary effect of pain-related avoidance of movement and can itself contribute to worsening pain and function over time.
Pre-Exercise Safety Checklist
Before beginning this routine, run through this quick checklist.
- [ ] I do not have any of the warning signs listed in the “When You Should See a Doctor First” section (recent significant injury, inability to bear weight, significant or rapidly developing swelling, visible deformity, severe or worsening pain, signs of infection, numbness or weakness, or a locked knee).
- [ ] If I have had recent knee surgery, I am following my surgeon’s or physical therapist’s specific protocol rather than this general guide, or I have received clearance to use this guide alongside my prescribed program.
- [ ] If I have a diagnosed ligament or meniscus injury that has not yet been evaluated for exercise appropriateness, I plan to check with a healthcare provider first.
- [ ] I have a sturdy chair, access to a wall, and a comfortable surface to exercise on.
- [ ] I understand the general pain guideline (mild discomfort that settles within about an hour is generally acceptable; sharp, severe, or worsening pain is a signal to stop and reassess).
- [ ] I plan to start at a conservative volume and progress gradually, rather than beginning at the most advanced level described for each exercise.
- [ ] I have a plan for tracking my progress, even informally, so I can assess how the routine is working over the coming weeks.
14 Daily Habits for Long-Term Knee Health
Beyond the structured routine itself, these small daily habits support the underlying goals of this program, strength, mobility, and consistent movement, and are worth building into your regular life over time.
Three Common Scenarios and How to Adapt Your Routine
These illustrative scenarios show how the same core routine can be adapted to different everyday situations. They are general examples meant to illustrate the adaptation process, not individual case studies or guarantees of specific outcomes.
Scenario: Someone With a Desk Job and Stiff Knees by the End of the Day
A common pattern involves relatively comfortable knees in the morning that become increasingly stiff and achy by the afternoon or evening, often related to prolonged sitting combined with general deconditioning. A reasonable approach would combine the seated modifications described earlier (seated quad sets and seated straight leg raises performed periodically throughout the workday) with the full routine performed in the evening, 4 to 5 days per week, along with a goal of standing and moving briefly every 30 to 60 minutes during work hours. Over several weeks, this combination of frequent gentle movement during the day and consistent strengthening in the evening commonly helps reduce the end-of-day stiffness pattern.
Scenario: Someone With Morning Stiffness Related to Arthritis
A pattern of significant stiffness upon waking that gradually eases over 15 to 30 minutes with movement is a classic presentation associated with osteoarthritis. A reasonable approach would include a very gentle warm-up immediately upon waking (such as ankle circles and gentle knee bends performed while still seated on the edge of the bed), followed by the quick routine later in the morning once stiffness has eased somewhat, and the full routine performed later in the day, 3 to 4 days per week, when the joint typically feels more comfortable and ready for more demanding exercise.
Scenario: Someone With Recurring Soreness After Weekend Hikes
A pattern of knee discomfort that reliably appears after longer or more demanding hikes, but is otherwise minimal during regular daily activities, often reflects a mismatch between current strength levels and the specific demands of hiking, particularly downhill sections, which place significant eccentric (lengthening) demand on the quadriceps. A reasonable approach would emphasize the full routine 4 to 5 days per week in the lead-up to planned hikes, with particular attention to progressing step-ups (which mimic some of the demands of uneven terrain and elevation changes) and wall sits, along with considering trekking poles for additional stability and reduced knee loading during the hike itself, particularly on downhill sections.
A Few More Frequently Asked Questions
Can I do this routine if I have both knee pain and lower back pain?
Many of the exercises in this guide, particularly the floor-based ones, can be adapted for lower back comfort; for example, keeping the resting leg’s knee bent with the foot flat on the floor during straight leg raises (as noted in the exercise instructions) helps support the lower back. If lower back pain is a significant, separate concern, it may be worth addressing with your healthcare provider alongside your knee rehabilitation, since the two can sometimes be related through shared muscle groups and movement patterns.
Is it better to do all 7 exercises in one session, or spread them throughout the day?
Both approaches are reasonable and research does not strongly favor one over the other for general strengthening purposes. Completing the full routine in one session is often more time-efficient and easier to build into a consistent daily habit, while spreading exercises throughout the day (as suggested for the quick routine or for quad sets specifically) can be helpful for those managing significant pain, limited single-session tolerance, or simply a preference for shorter, more frequent movement breaks.
What if I have had a meniscus tear, can I still do these exercises?
This depends significantly on the specific type, size, and location of the tear, as well as whether it has been surgically repaired, and should be guided by your orthopedic provider or physical therapist, since meniscus tears vary considerably in their treatment approach. Many meniscus-related rehabilitation programs do include strengthening exercises similar to those in this guide, but the specific timing and progression should be individualized to your situation rather than following this general guide alone.
Can weak core muscles contribute to knee pain?
Some research suggests that core and trunk stability can influence overall movement patterns and alignment through the lower body, including the knees, though the knee-specific research is less extensive than the hip-focused research discussed throughout this guide. A generally strong, stable core is a reasonable complementary goal as part of an overall strength and movement program, though it is not the primary focus of this knee-specific guide.
Does cold weather make knee pain worse, and does that mean I should exercise less in winter?
Many people with joint pain, particularly arthritis-related pain, report that their symptoms feel worse in cold or damp weather, though the scientific evidence specifically linking weather changes to objective joint inflammation is mixed and not fully understood. Regardless of the exact mechanism, if you notice this pattern, it does not mean you should exercise less; if anything, maintaining consistent exercise through colder months, with an extra emphasis on warming up thoroughly beforehand, is generally still recommended and may help offset some of the stiffness commonly reported in colder weather.
Can yoga or Pilates help alongside this routine?
Many yoga and Pilates practices incorporate movements that overlap with the goals of this guide, building strength, improving flexibility, and developing body awareness, and some research supports these practices as beneficial for various musculoskeletal conditions, including some knee pain presentations. If you enjoy yoga or Pilates, choosing a class or instructor experienced in modifications for knee pain, and being mindful of deep knee-bending poses that may need modification (similar to the guidance on deep squats in this guide), can allow you to incorporate these practices alongside the targeted strengthening routine described here.
I feel like my “good” knee is starting to hurt too, is that related?
This is a commonly reported pattern, sometimes related to compensating for the originally painful knee by shifting more weight, effort, or movement strategy onto the other side over time, which can place additional strain on that leg. This is part of why this guide recommends exercising both legs, even when pain is initially isolated to one side, to help maintain balanced strength and reduce the likelihood of this compensatory pattern developing or worsening.
How do I stay motivated to keep doing this routine long-term?
Common strategies that support long-term adherence include tracking progress (as described in this guide) to make gradual improvements visible, attaching the routine to an existing daily habit, focusing on functional goals that matter to you personally (such as a specific activity you want to return to) rather than abstract exercise goals, and allowing some flexibility in how and when you complete the routine, using the shorter “quick routine” on days when the full version feels like too much, rather than skipping entirely.
Two Extra Mini-Routines: Morning and Desk Versions
For those who want quick, targeted options beyond the main daily and quick routines described earlier, these two mini-routines address two of the most commonly reported situations: morning stiffness and prolonged desk sitting.
The 5-Minute Morning Stiffness Routine
Designed to be done while still in bed or seated at the bedside, before standing up for the day.
- Ankle circles: 10 in each direction, each foot, performed while lying or seated.
- Gentle knee bends (lying down): Slowly slide one heel toward your glutes and back (a lying heel slide), 8 to 10 times per leg, moving gently and well within a comfortable range.
- Seated or lying quad sets: 8 to 10 reps per leg, 5-second holds.
- Gentle hip circles (lying on your back, knees bent): Let both bent knees gently fall a few inches side to side, 8 to 10 times, to loosen the hips before standing.
- Stand up slowly, holding onto support if needed, and take a few moments to walk gently in place or around the room before moving into your normal morning routine.
This short sequence is designed to gently mobilize the knees and surrounding joints before asking them to bear full weight for the day, which many people with morning stiffness find more comfortable than standing up abruptly after a night of stillness.
The 4-Minute Desk Break Routine
Designed to be done discreetly at or near your desk during a short work break, requiring no equipment and minimal space.
- Seated marching: Alternate lifting each knee toward your chest, 10 times per leg.
- Seated quad sets: 8 reps per leg, 5-second holds, performed with the leg extended under or in front of the desk.
- Seated straight leg raises (leg extensions): 8 reps per leg, as described in the chair-based modifications section.
- Standing calf raises (holding the desk for balance, if needed): Rise onto your toes and lower back down, 10 repetitions, which gently engages the lower leg and encourages circulation after prolonged sitting.
- A brief standing stretch or short walk, even just to a water cooler and back, to break up the sitting period.
Performing this short routine every 1 to 2 hours during a desk-based workday can meaningfully reduce the stiffness and discomfort that often builds from prolonged sitting, complementing the main strengthening routine performed at a dedicated time each day.
Matching Exercises to Your Specific Pain Pattern
While all 7 exercises in this guide work together as a complete routine, understanding which exercises most directly address which common pain patterns can help you prioritize, particularly in the early weeks when doing the full routine may feel like a lot.
| If your pain is mainly… | Prioritize these exercises |
|---|---|
| Around or behind the kneecap, worse with stairs or sitting | Straight leg raises, wall sits (shallow range), clamshells |
| Along the outside of the knee, worse with running/hiking | Clamshells, hamstring curls |
| General stiffness, worse in the morning or after rest | Heel slides, quad sets, gentle full routine |
| Worse going down stairs specifically | Step-ups (controlled, slow tempo), straight leg raises |
| Worse standing up from a low chair | Wall sits, step-ups, quad sets |
| Accompanied by a feeling of instability or “giving way” | Clamshells, hamstring curls, straight leg raises (and consider professional evaluation, since instability can sometimes indicate a ligament issue worth assessing) |
This table is a general starting guide for prioritization, not a strict prescription; most people benefit from including all 7 exercises as described in the main routine over time, using this table simply to decide where to place extra initial emphasis or which exercises to introduce first if starting very gradually.
What to Include in Your Own Printable Quick-Reference Sheet
If you want a simple, printable version of this routine to keep near your exercise space, here is what to include, condensed from this guide:
- The 7 exercises, listed with their starting sets/reps (summarized in the quick reference table earlier in this guide).
- The general pain guideline: mild discomfort that settles within about an hour is generally fine; stop and reassess for sharp, severe, or worsening pain.
- Your weekly schedule (full routine days vs. quick routine days), based on the sample schedule or your own adjusted version.
- A simple tracking log, using the weekly template provided earlier in this guide, with space for pain level, functional notes, and exercise days completed.
- The warning signs that warrant medical attention, condensed from the “When You Should See a Doctor First” section, as a quick safety reminder.
(Editor’s note for FitHealthyMind.com: this reference sheet concept works well as a one-page printable graphic or a simple downloadable PDF companion to this article, similar in spirit to the free PDF offered in your vegan weight loss guide, if you’d like to build a lead magnet around this content as well
Distinguishing Similar-Sounding Knee Conditions
Because so many knee conditions share overlapping symptoms, it’s easy to get confused by terminology. Here is a brief, general overview of how a few commonly confused conditions differ. This is educational information only and is not a substitute for professional diagnosis, since accurately distinguishing between these conditions typically requires a physical examination and, in some cases, imaging.
Osteoarthritis vs. Rheumatoid Arthritis
Osteoarthritis is a “wear and tear” condition involving gradual cartilage breakdown, typically developing slowly over years and most common in older adults, usually affecting one or a few joints asymmetrically. Rheumatoid arthritis is an autoimmune inflammatory condition where the immune system attacks the joint lining, typically causing more pronounced morning stiffness (often lasting more than an hour), symmetrical joint involvement (affecting the same joints on both sides of the body), and sometimes systemic symptoms like fatigue; it often requires different treatment approaches, including specific anti-inflammatory and immune-modulating medications, alongside exercise therapy, which remains beneficial for both conditions.
Tendinitis vs. Ligament Sprain
Tendinitis refers to irritation or inflammation of a tendon (the tissue connecting muscle to bone), such as patellar tendinitis, which causes pain typically localized to the tendon itself (often just below the kneecap for patellar tendinitis) and is usually related to overuse or repetitive loading. A ligament sprain refers to a stretching or tearing injury of a ligament (the tissue connecting bone to bone), such as an MCL or ACL sprain, which is typically related to a specific traumatic event (such as a twisting injury or direct blow) rather than gradual overuse, and may be accompanied by swelling, instability, or a “pop” sensation at the time of injury.
Patellofemoral Pain Syndrome vs. Chondromalacia Patella
These terms are sometimes used interchangeably, though chondromalacia patella technically refers specifically to softening or damage of the cartilage on the underside of the kneecap, which may or may not be present in someone experiencing the broader symptom pattern described as patellofemoral pain syndrome. In practice, many of the same contributing factors (quadriceps and hip weakness, kneecap tracking issues) and the same general treatment approach (the strengthening exercises in this guide) apply to both.
Meniscus Tear vs. General Joint Line Pain
A meniscus tear refers to a specific tear in one of the C-shaped cartilage structures within the knee, which can occur from a specific twisting injury or can develop more gradually, particularly in older adults with age-related cartilage changes, and may cause symptoms like catching, locking, or a sensation of the knee “giving way,” in addition to pain along the joint line. Not all pain along the joint line indicates a meniscus tear; this symptom can also relate to other structures, including early osteoarthritis changes, which is part of why joint line pain, particularly with any catching, locking, or instability, often warrants professional evaluation rather than assumption based on symptoms alone.
Bursitis vs. Arthritis
Bursitis refers to inflammation of one of the small fluid-filled sacs (bursae) that cushion areas around the knee joint, such as prepatellar bursitis (sometimes called “housemaid’s knee”), often related to repetitive kneeling or direct pressure, causing localized swelling and tenderness, often more superficial and localized than the deeper, more diffuse ache commonly associated with arthritis. Both conditions can benefit from general knee-supportive strengthening, though bursitis may also require specific attention to avoiding the aggravating pressure or kneeling activity during the acute phase.
Putting It All Together: A Realistic Month-by-Month Outlook
To help set appropriate expectations, here is a general outline of what a consistent approach to this routine commonly looks like over the first few months. Individual experiences vary considerably, and this is a general illustration rather than a guarantee.
Month 1: Building the Foundation
The primary focus during month 1 is establishing consistent practice and learning correct form, following the 4-week progression plan outlined earlier in this guide. Many people notice early signs of improvement during this period, such as slightly reduced morning stiffness or a growing sense of confidence with movements that previously felt concerning, though significant pain reduction is not always apparent yet, and that is entirely normal at this stage.
Month 2: Noticeable Functional Changes
By month 2, with consistent practice, many people begin noticing more tangible functional improvements: stairs feeling more manageable, standing from a chair requiring less effort, or being able to walk further before discomfort sets in. This is also a reasonable point to begin progressing exercises further (increased resistance, increased volume) if the current level feels well-controlled and comfortable, following the progression guidance provided for each exercise.
Month 3 and Beyond: Integration Into Daily Life
By this point, many people have developed enough strength and confidence to begin more comfortably reintroducing activities they may have scaled back due to pain, such as longer walks, hikes, or recreational sports, following the gradual reintroduction principles discussed in the “Exercises and Movements to Be Cautious With” section. The routine itself often becomes a more automatic, lower-effort habit by this stage, and many people transition to a maintenance mindset, continuing a version of the routine (perhaps 3 to 4 days per week rather than daily) as an ongoing part of their general fitness and joint health practice, rather than viewing it as a temporary “fix.”
If Progress Stalls
If, despite consistent practice over 2 to 3 months, you are not noticing meaningful improvement, or if symptoms are worsening rather than improving, this is a clear and reasonable point to seek a professional evaluation, if you have not already, since there may be a more specific underlying issue that benefits from individualized assessment and treatment beyond what a general home exercise guide can address.
Combining This Routine With Other Forms of Exercise
This knee-focused routine is designed to complement, not replace, a generally active lifestyle. Here is how it fits alongside other common forms of exercise.
Walking
As mentioned throughout this guide, regular walking is generally well-supported as a beneficial, low-impact activity for most people with knee pain, and pairs naturally with this strengthening routine. Many people find that as their strength improves through this routine, their walking tolerance (distance and comfort) improves alongside it, creating a positive cycle. Starting with shorter, more frequent walks and gradually building duration, rather than attempting a long walk before building adequate strength, is a reasonable approach for those currently experiencing significant pain.
Swimming and Water-Based Exercise
As noted in the section on arthritis-related stiffness, water-based exercise is often particularly well-tolerated for knee pain, since the buoyancy of water significantly reduces the load on the joints while still providing resistance for cardiovascular and muscular benefit. If accessible to you, water walking, swimming, or water aerobics classes can be a valuable complement to this land-based strengthening routine, particularly during periods of significant pain when land-based cardio feels too demanding.
Cycling
Stationary or outdoor cycling, particularly with the seat height set appropriately (a seat that is too low increases knee strain), is often well-tolerated for many common knee conditions and provides cardiovascular benefit with relatively low joint impact compared with running. If cycling aggravates your knee pain, checking bike fit (seat height and position) is a reasonable first troubleshooting step, and if pain persists despite proper fit, this is worth discussing with a healthcare provider or physical therapist.
General Strength Training
If you participate in broader strength training beyond this knee-focused routine, the principles discussed throughout this guide, appropriate progression, attention to form, and responsiveness to pain signals, apply equally to other lower-body exercises like squats, lunges, and leg presses. This routine’s exercises can serve as a useful foundation and warm-up before more demanding lower-body strength training, and the hip-focused exercises in particular (clamshells) are commonly recommended as an activation exercise before squats or lunges in many strength training programs, regardless of whether knee pain is present.
Running
As discussed in the “Knee Pain Exercises for Specific Situations” section, this routine, particularly the hip-strengthening components, is commonly used as part of injury management and prevention programs for runners. For those currently managing knee pain, temporarily reducing running volume while building strength through this routine, then gradually and carefully reintroducing running volume, is a commonly recommended approach, ideally with guidance from a running-specific coach or physical therapist for a more individualized return-to-running plan.
Avoiding Overload
If you are incorporating this routine alongside other significant forms of exercise, pay attention to your overall training load and recovery, since even beneficial exercise can become excessive if layered without adequate recovery time, particularly during the early weeks of a new routine when your body is still adapting. The general principle of gradual, consistent progression applies to your overall activity level, not just this specific routine in isolation.
An Equipment-Free Travel Version of the Routine
For days when you are traveling, away from your usual exercise space, or simply want the most minimal possible version of this routine, here is a stripped-down version requiring no equipment at all, not even a chair, designed to be done in a hotel room or similarly small space.
- Quad sets: 10 reps per leg, 5-second holds, performed lying on a bed or floor.
- Straight leg raises: 10 reps per leg, performed lying on a bed or floor.
- Heel slides: 10 reps per leg, performed lying on a bed or floor.
- Clamshells: 10 reps per side, performed lying on your side on a bed or floor.
- Standing hamstring curls: 10 reps per leg, holding onto a wall, doorframe, or sturdy piece of furniture for balance.
- Mini wall sit: One hold of 10 to 15 seconds, using any available wall.
- Step-up alternative: If no step is available, perform standing marches instead (alternating high knee lifts while standing, holding support if needed), 15 reps per leg, as a substitute that still engages similar muscle groups, even without the specific step-up pattern.
This travel version takes about 8 to 10 minutes and requires nothing beyond a bed, floor, and wall, making it realistic to maintain even during travel, which helps preserve the consistency that matters so much for long-term results, as discussed throughout this guide.
Key Takeaways
- Exercise, particularly targeted strengthening, is one of the most well-supported, effective approaches for common causes of knee pain, including osteoarthritis, patellofemoral pain, and IT band syndrome, often more effective than rest alone.
- The 7 exercises in this guide, quad sets, straight leg raises, wall sits, step-ups, hamstring curls, clamshells, and heel slides, target the muscle groups most consistently linked to knee support and function in physical therapy research: the quadriceps, hamstrings, and hip stabilizers, along with knee range of motion.
- Consistency matters more than intensity. A moderate, sustainable routine performed regularly over 6 to 8 weeks or longer tends to produce better results than an intense but inconsistent approach.
- Mild discomfort during exercise is generally acceptable; sharp, severe, or worsening pain is not. Use this general guideline to gauge whether an exercise or progression is appropriate.
- Certain warning signs, a recent significant injury, inability to bear weight, significant swelling, instability, or signs of infection, warrant prompt medical evaluation rather than starting a home exercise program.
- This routine can be adapted to different fitness levels, pain levels, and specific situations, from chair-based modifications to travel-friendly versions, making it accessible across a wide range of circumstances.
- Tracking your progress, even informally, helps you recognize gradual improvement and provides valuable information if you need to consult a healthcare provider.
- This guide is educational, not a substitute for individualized medical or physical therapy care, particularly for persistent, severe, or unclear knee pain.
How This Guide Was Informed
The exercises, general principles, and recommendations in this guide are grounded in the broader body of physical therapy and orthopedic research on exercise for common knee pain conditions, reflecting approaches widely used in clinical practice and consistent with guidance from major professional bodies in this space, including orthopedic, sports medicine, and rheumatology organizations that publish clinical guidelines for conditions like knee osteoarthritis and patellofemoral pain. This guide draws on well-established, broadly accepted principles, strengthening the quadriceps, hamstrings, and hip stabilizers; maintaining range of motion; and progressing gradually, rather than niche or unproven approaches, in order to provide a reliable, general-purpose starting point. It is not based on, and does not constitute, a review of your individual medical history or a personalized clinical assessment, which only a qualified healthcare provider examining you directly can provide.
A Note on Individual Variation
Research on exercise therapy for knee pain, like most medical and rehabilitation research, reports outcomes across groups of people, showing that, on average, structured strengthening programs produce meaningful improvement for most participants. This does not guarantee that every individual will respond identically; some people improve more quickly, some more slowly, and in a small proportion of cases, a general approach like this one may not sufficiently address the specific underlying cause of an individual’s pain, which is part of why this guide repeatedly emphasizes seeking professional evaluation when progress stalls or when warning signs are present, rather than presenting itself as a universal solution.
A Few More Questions Worth Addressing
Can I use a foam roller on my knees or the surrounding muscles?
Foam rolling the muscles around the knee, such as the quadriceps, hamstrings, and the outer thigh (often marketed as “IT band rolling,” though the IT band itself is a dense, relatively inelastic structure that is not meaningfully lengthened by rolling), is a commonly used self-massage technique that some people find helpful for general muscle tension and comfort. It is generally considered a reasonable, low-risk complementary practice, though, similar to other passive treatments discussed earlier in this guide, it is not a substitute for the active strengthening exercise that has stronger evidence for addressing the underlying contributors to most knee pain.
Should I exercise on days when my knee feels unusually painful, even without a specific new injury?
On days with notably increased pain without a clear new cause, it is generally reasonable to perform the gentlest exercises in this guide (quad sets and heel slides) at a reduced volume, rather than either pushing through the full routine or skipping movement entirely, following the general modification guidance provided earlier for significant current pain. If this pattern of unpredictable, significant pain flares becomes frequent or severe, it is worth discussing with a healthcare provider to better understand what may be driving these fluctuations.
Is it better to exercise before or after a long walk or demanding activity?
There is no single universally correct order, and reasonable approaches vary by individual preference and how your knee tends to respond. Some people prefer performing this strengthening routine before a demanding activity, as a form of activation and warm-up, while others prefer doing it afterward, as a way to reinforce the muscles that were just used, or on an entirely separate day to allow adequate recovery between a demanding activity and additional strengthening work. Paying attention to how your knee responds to different sequencing over a few weeks can help you identify what works best for you personally.
Can poor hip or ankle mobility contribute to knee pain, even if the hip or ankle itself doesn’t hurt?
Yes, this is a commonly discussed concept in physical therapy, sometimes referred to as a “kinetic chain” issue, where limited mobility or control at a joint above (the hip) or below (the ankle) the knee can alter movement patterns in a way that increases strain specifically at the knee, even when the hip or ankle itself remains symptom-free. This is part of why this guide includes hip-focused exercises even for knee-specific pain, and it is also why a comprehensive physical therapy evaluation, which can assess mobility and control throughout the whole lower-body kinetic chain, can sometimes identify contributing factors beyond the knee itself that a knee-only approach might miss.
Will building muscle around my knee make the joint look bigger or bulkier?
The strengthening volumes and exercise types in this guide are designed for functional strength and pain relief, not significant muscle size (hypertrophy) goals, which generally require substantially higher training volumes and resistance than what is outlined here. Most people following this routine will not notice a significant change in the visual size of their thigh muscles; the primary changes are in strength, control, and how the knee feels and functions during daily activities, rather than noticeable changes in muscle bulk.
The 7 Best Exercises for Knee Pain Relief
Do these exercises daily for the best results. Each one takes 1-2 minutes. The full routine is about 15 minutes.
Exercise 1: Straight Leg Raise

What it does: Strengthens your quadriceps (front thigh) without bending your knee. This is the #1 exercise physical therapists prescribe for knee pain.
How to do it:
- Lie on your back on a mat or carpet.
- Bend your left knee, keeping your foot flat on the floor.
- Keep your right leg straight, toes pointing up.
- Tighten your right thigh muscle.
- Slowly lift your right heel about 6-12 inches off the floor.
- Hold for 2-3 seconds, keeping the leg straight.
- Lower slowly.
- Repeat 10 times, then switch legs.
Pro tip: Don’t arch your back. Keep your core gently engaged. If lifting the leg feels hard, that’s good—it means your muscle is working.
Exercise 2: Glute Bridge

What it does: Wakes up your glutes (butt muscles). Strong glutes take pressure off your knees during walking, squatting, and climbing.
How to do it:
- Lie on your back, knees bent, feet flat on the floor, hip-width apart.
- Arms rest at your sides, palms down.
- Squeeze your glutes and lift your hips toward the ceiling.
- Your body should form a straight line from shoulders to knees.
- Hold for 2-3 seconds, squeezing tight.
- Lower slowly back down.
- Repeat 10-15 times.
Pro tip: Don’t let your lower back do the work. Focus on squeezing your butt. If you feel it in your lower back, lower your hips slightly.
Exercise 3: Seated Knee Extension

What it does: Isolates the quadriceps, building strength exactly where your knee needs it most.
How to do it:
- Sit on a sturdy chair, back straight.
- Extend your right leg straight out in front of you, heel on the floor.
- Tighten your thigh muscle.
- Slowly lift your foot off the floor until your leg is straight (or as straight as comfortable).
- Hold for 2-3 seconds.
- Lower slowly.
- Repeat 10 times, then switch legs.
Pro tip: Go slow. The control on the way down is where the strength is built. If this is too easy, add a light ankle weight (or a bag of beans tied around your ankle).
Exercise 4: Wall Sit

What it does: Builds endurance in your quads, glutes, and calves. Excellent for preparing your knees for real-life activities like gardening, skiing, or just standing for long periods.
How to do it:
- Stand with your back against a wall, feet shoulder-width apart.
- Walk your feet out about 2 feet from the wall.
- Slide your back down the wall until your knees are bent at about a 45-degree angle. (Don’t go to 90 degrees if it hurts.)
- Hold this position for 15-30 seconds.
- Slowly slide back up.
- Repeat 3-5 times.
Pro tip: Keep your knees directly above your ankles—not caving inward. If you feel pain, don’t go as low. Even a slight bend works.
Exercise 5: Hamstring Curl (Standing)

What it does: Targets the hamstrings (back of thigh), which are often weak and overlooked. Strong hamstrings balance the pull on your knee joint.
How to do it:
- Stand behind a sturdy chair, holding the back for balance.
- Shift your weight onto your left leg.
- Slowly bend your right knee, bringing your heel toward your butt.
- Keep your thighs lined up (don’t move your knee forward).
- Hold for 2 seconds.
- Lower slowly.
- Repeat 10 times, then switch legs.
Pro tip: Go slow. Don’t swing your leg. Imagine you’re pressing your heel into a pillow.
Exercise 6: Calf Raises
What it does: Strengthens your calves, which support your ankle and indirectly affect your knee alignment.
How to do it:
- Stand behind a sturdy chair, holding the back for balance.
- Keep your legs straight but not locked.
- Slowly rise onto your tiptoes as high as comfortable.
- Hold for 2 seconds.
- Lower slowly back down.
- Repeat 15-20 times.
Pro tip: Do this on a flat floor first. When it gets easy, try standing on the edge of a stair (holding the railing) for a deeper stretch.
Exercise 7: Step-Ups (Low Height)
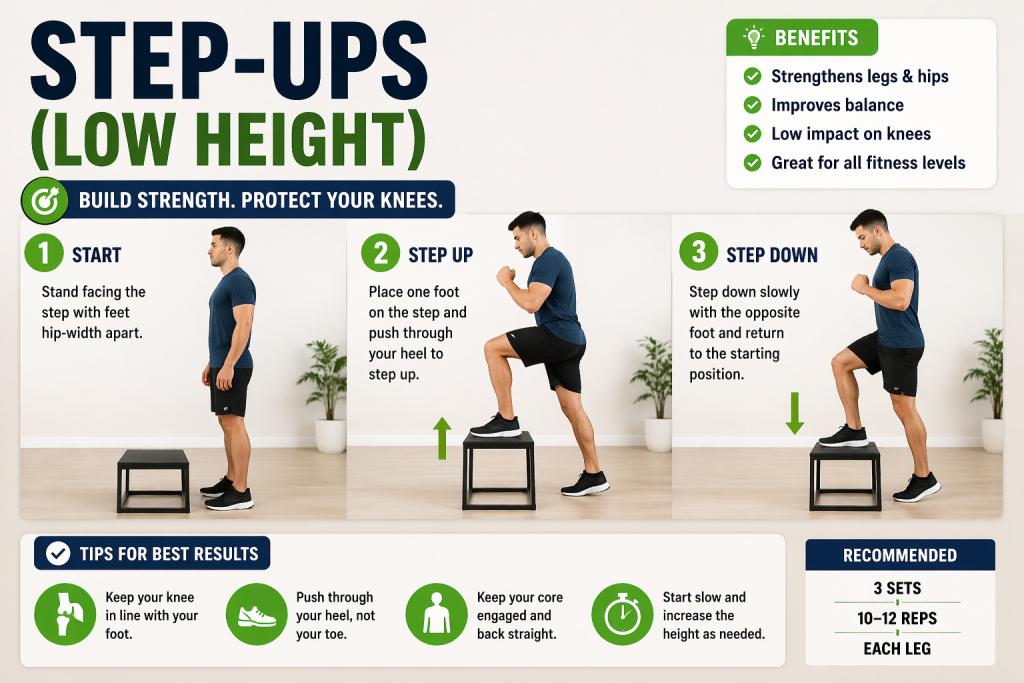
Final Thoughts: Building Stronger, More Resilient Knees
Knee pain can feel discouraging, especially when it starts limiting activities you once did without a second thought. But the research is clear and consistent: for most common causes of knee pain, the knee joint is not something you need to simply protect by avoiding movement indefinitely. It is something you can actively support, strengthen, and improve through consistent, appropriately chosen exercise.
The seven exercises in this guide, quad sets, straight leg raises, wall sits, step-ups, hamstring curls, clamshells, and heel slides, were not chosen arbitrarily. They represent a well-rounded approach grounded in the same principles used in physical therapy clinics for a wide range of knee conditions: build quadriceps and hamstring strength to better absorb and control load through the joint, build hip strength (particularly the gluteus medius) to improve alignment and control during movement, and maintain comfortable range of motion to reduce stiffness. Together, they address the most consistently identified contributors to common knee pain patterns, from osteoarthritis to patellofemoral pain to IT band syndrome.
None of this requires a gym membership, expensive equipment, or hours of your day. It requires a sturdy chair, a wall, about 10 to 25 minutes depending on which version of the routine you choose, and, more than anything, consistency over the coming weeks. Most research points to a 6- to 8-week timeline before meaningful improvement becomes clearly noticeable, which can feel like a long time when you are dealing with pain today, but is a realistic and achievable timeline for lasting change, especially compared with approaches that offer only temporary relief without addressing the underlying strength and movement patterns involved.
Start where you are. If your pain is significant right now, begin with the gentlest exercises and the modifications designed for that situation, and build from there. If your pain is mild and you are mainly looking to build strength and prevent future issues, start at a more moderate pace and progress steadily. Either way, pay attention to your body’s signals throughout, use the troubleshooting guidance in this article when something does not feel right, and do not hesitate to involve a healthcare provider or physical therapist, particularly if you notice any of the warning signs discussed, or if progress stalls despite consistent effort.
Your knees carry you through an enormous number of daily movements, often without much conscious thought, until pain makes you notice every single one. Investing a consistent, modest amount of time into strengthening and supporting them is one of the most evidence-backed, accessible things you can do to work toward moving through your days with less pain and more confidence.
Choose your starting point from this guide, mark your calendar, and begin today.
Medical Disclaimer
The information in this article is provided for general educational purposes only and is not intended as medical advice, physical therapy advice, or a substitute for professional evaluation, diagnosis, or treatment. It does not create a doctor-patient, physical therapist-patient, or other professional care relationship. Knee pain can have many underlying causes, some of which require specific medical evaluation and treatment that a general exercise guide cannot provide. Always consult a qualified healthcare provider, such as a doctor or licensed physical therapist, before starting any new exercise program, particularly if you have a recent injury, significant or worsening pain, swelling, instability, numbness, signs of infection, or any of the other warning signs described in this article, or if you have an existing medical condition that may affect your ability to exercise safely. Stop any exercise that causes sharp, severe, or worsening pain, and seek medical attention if needed. Individual results from following this routine will vary, and no specific outcome is guaranteed.
2 thoughts on “7 Knee Pain Exercises That Actually Help (Do These Daily for Relief)”